
The short answer is yes. All-on-4 treatment in Turkey at Aylan Clinic allows patients from Toronto, Montreal, Vancouver, Calgary, Ottawa and across Canada to replace a full arch of teeth on four implants, with a fixed bridge, for up to 60% less than Canadian private prices. It is a full-arch solution delivered over two trips: you leave the first with a fixed temporary bridge, and the definitive bridge is fitted months later once the implants have integrated.
This guide complements our All-on-4 in Turkey procedure page, and sits within our wider dental care in Turkey section. Below you will find how the technique works, who it suits, the honest timeline, the assessment that should never be skipped, recovery, cleaning, materials, aesthetics, risks, costs and the questions that discriminate a good clinic from a poor one. At any time you can see pricing in Turkey, with no obligation.
Three Things That Belong at the Top
First: you will leave your first trip with a temporary bridge, not your final teeth. All-on-4 is designed to give you functioning teeth immediately, which is genuinely one of its great advantages. But the definitive bridge comes months later, on a second trip. Any offer implying that one week completes the treatment is describing the temporary.
Second: All-on-4 is a full-arch solution. It is not for someone missing three or four teeth. It is for someone whose arch is failing or already edentulous, and who is prepared to have any remaining teeth in that arch removed.
Third: the term “All-on-4” is a specific technique, not a generic label. It involves tilting the two posterior implants to exploit available bone and avoid grafting. Some clinics use the name loosely. It is worth knowing what you are actually being offered.
1. Understanding All-on-4
What is All-on-4?
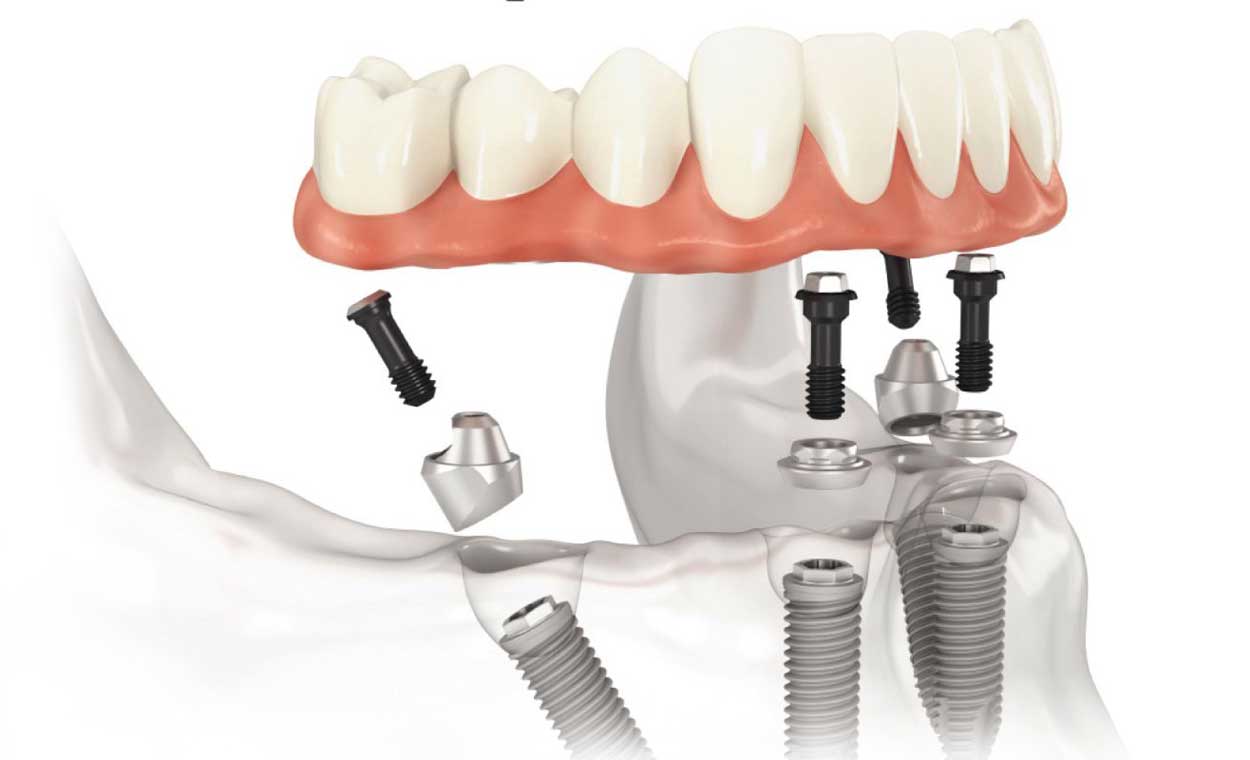
A full-arch fixed bridge supported by four implants. Two are placed vertically at the front of the jaw, where bone is usually denser and more abundant. Two are placed at the back at an angle — typically thirty to forty-five degrees — which allows them to engage more bone and to bypass anatomical obstacles. The bridge is then screwed onto these four implants. It does not come out. You clean it in place, like natural teeth.
Why are the back implants tilted?
This is the central idea of the technique, and it solves two specific problems. In the upper jaw, tilting allows the implant to pass in front of the maxillary sinus rather than into it — which is what would otherwise require a sinus lift and many additional months. In the lower jaw, tilting allows the implant to sit forward of the nerve canal while still engaging enough bone to be stable.
Tilting also spreads the implants further apart along the arch, which improves the mechanical support for a long bridge. Four well-distributed implants can carry a full arch; four bunched together at the front could not.
What does it replace?
A full arch — typically ten to fourteen teeth on the bridge, depending on design. It can be done on the upper jaw, the lower jaw, or both.
Who is it for?
Three profiles account for most cases:
- Patients already wearing a denture who want something fixed. This is the largest group, and often the most satisfied.
- Patients with a failing arch — advanced gum disease, multiple loose or broken teeth, extensive decay — where individual teeth cannot realistically be saved.
- Patients missing most of an arch with a few remaining teeth that are not strategically useful.
Who is it not for?
Someone missing a few teeth. If you have eight healthy teeth in an arch, All-on-4 means removing them. That is a serious decision and rarely the right one. Individual implants or a conventional bridge are usually more appropriate, and a clinic proposing full-arch extraction for a partially intact arch should be questioned closely. We say this plainly because it is the most consequential over-treatment in implant dentistry.
2. All-on-4 Versus Other Options
All-on-4 versus individual implants
Replacing twelve teeth with twelve implants would be prohibitively expensive and often anatomically impossible. All-on-4 achieves a full arch with four. The trade-off is that the teeth are joined in one bridge rather than being independent.
All-on-4 versus All-on-6
Six implants distribute forces across more support points, which some clinicians prefer, particularly in the upper jaw where bone is softer. All-on-4 is less invasive, less expensive, and has substantial published evidence behind it. Neither is universally superior. The choice depends on your bone quality and quantity, your bite forces, and whether you grind. Both options are covered in dedicated guides, and a good clinic will explain why it is recommending one for you specifically.
All-on-4 versus an implant-retained denture
This comparison deserves more attention than it usually receives, because the cost difference is substantial. An implant-retained overdenture clips onto two to four implants. It comes out for cleaning. It is dramatically more stable than a conventional denture — patients who could not keep a lower denture in place often describe it as life-changing — and it costs considerably less than All-on-4. All-on-4 is fixed. It does not come out, feels more like natural teeth, and preserves more chewing efficiency. If budget is a real constraint, ask about the overdenture option before dismissing it. For a lower arch in particular, it delivers a large proportion of the benefit at a fraction of the cost.
All-on-4 versus a conventional denture
A conventional upper denture can work reasonably well, since it gains suction from the palate. A conventional lower denture is notoriously unstable, because there is no palate and the tongue displaces it. This asymmetry explains a pattern we see often: patients tolerate their upper denture but cannot manage the lower one. In those cases, treating the lower arch alone — with All-on-4 or an overdenture — often solves the actual problem at half the cost of doing both.
3. The Honest Timeline
What happens on trip one?
Assessment with CBCT imaging, extraction of any remaining teeth in the arch, placement of four implants, and fitting of a temporary fixed bridge, usually on the same day or the day after. You leave with teeth. This is real and it matters — patients who dread the idea of being toothless are reassured to learn it does not happen.
What is the temporary bridge like?
It is fixed, it functions, and it looks acceptable. It is usually made of acrylic. It is not as strong, as refined or as aesthetically precise as the definitive bridge. Practical implications: you will be asked to avoid hard and crunchy foods for months. Acrylic can chip or fracture under heavy load, and a broken temporary is inconvenient — which is why we insist you identify a Canadian dentist before travelling.
How long do I wear it?
Three to six months, while osseointegration completes. This period cannot be shortened; it is bone biology.
What happens on trip two?
Integration is confirmed radiographically. Impressions or a digital scan are taken. A try-in allows you to approve the shape, shade and length. The definitive bridge is then fitted, with adjustment appointments over the following days.
So the total is about a year?
Roughly. Two trips, three to six months apart, plus planning time. Understand this from the outset, and be sceptical of any presentation that compresses it.
Why is the two-stage approach necessary at all?
Because loading four implants with a rigid, definitive bridge before they have integrated risks losing them. The temporary bridge is deliberately made of a material with some flexibility, which cushions the implants during healing. A definitive zirconia bridge is far more rigid and transmits force directly. This is not a commercial device to generate a second trip. It is the reason the technique works.
4. Why Canadians Consider Turkey
| Factor | Canada (private) | Turkey — Aylan Clinic |
|---|---|---|
| Cost | Very high for full-arch work | Up to 60% less, all-inclusive |
| Coverage | Annual maximums, typically $1,500–$3,000 | Same limitations; foreign care often excluded |
| Wait time | Variable | Rapid scheduling |
| Accommodation | Your responsibility | 5-star hotel, full board included |
| Companion | Additional cost | Free, accommodated and fed |
| Number of trips | None | Two |
Why is full-arch work where the price gap matters most?
Because the absolute numbers are large. A saving of a given percentage on a single crown is modest in dollar terms; the same percentage on two full arches is substantial. This is why All-on-4 is among the most common reasons Canadians look abroad for dental care.
Will Canadian insurance cover any of it?
Rarely a meaningful proportion, and the constraint is the annual maximum rather than outright exclusion. A full-arch case will exhaust several years of typical dental benefits. Practical steps: ask your insurer in writing whether foreign care is reimbursed and at what rate, request pre-determination, and insist on itemised invoicing listing each implant, each abutment and the prosthesis separately. A single-line “All-on-4 package” invoice is very difficult to claim against. If your treatment spans two calendar years, ask how your insurer dates a claim — you may be able to use two annual maximums.
5. Assessment: What Should Never Be Skipped
Why CBCT is mandatory here
More than for any single implant. All-on-4 depends on precise knowledge of where the sinus and the nerve canal are, because the whole technique consists of angling implants to avoid them while engaging maximum bone. A panoramic radiograph cannot provide that. It does not show bone width, it distorts, and it cannot map the nerve canal in three dimensions. A clinic planning All-on-4 without CBCT is guessing about the two structures the technique exists to avoid. This is not a corner that can be cut.
What else is assessed?
Remaining teeth and their prognosis, periodontal status, bone quality and quantity across the whole arch, your bite and jaw relationship, the amount of visible gum when you smile, lip support, and facial proportions. That last group matters more than patients expect. A full-arch bridge determines the position of your lip, the fullness of your face, and how much tooth shows when you smile. This is facial aesthetics, not just dentistry.
Is guided surgery used?
Increasingly. CBCT data can be used to plan implant positions digitally and to produce a surgical guide that transfers the plan to the mouth precisely. It is particularly valuable in All-on-4, where angulation is critical. Ask whether digital planning is used in your case. It is not universal and not always necessary, but a clinic that uses it is working to a plan rather than improvising.
What if I have very little bone?
Variants exist for severe bone loss, including longer implants engaging different bone structures. These are more complex procedures requiring specific expertise. If you have been told elsewhere that you have insufficient bone for any implant solution, it is worth a second assessment — but be equally cautious of a clinic that dismisses significant bone loss as unimportant.
6. What the Treatment Involves at Aylan Clinic
| Element | Detail |
|---|---|
| Implants | Four per arch, two vertical anterior, two tilted posterior |
| Extractions | Any remaining teeth in the treated arch |
| Temporary bridge | Fixed, fitted at trip one, worn 3–6 months |
| Definitive bridge | Fitted at trip two |
| Bridge materials | Zirconia, or titanium framework with ceramic or composite |
| Digital planning | CBCT-based, with surgical guide where indicated |
The clinical team
- Senior oral and maxillofacial surgeon — extractions and implant placement
- Prosthodontist — bridge design, try-in and fitting
- Implantology-focused dentist — planning and coordination
- Dental radiologist — CBCT interpretation
- In-house laboratory — same-day temporary fabrication and adjustments
What the package includes
- Free consultation and detailed treatment plan, no obligation
- 3D CBCT imaging on site
- Extractions of remaining teeth in the treated arch
- Four implants per arch, abutments, temporary bridge and definitive bridge
- 5-star hotel accommodation, full board
- A companion at no extra cost, accommodated and fed in the same room
- Airport–clinic–hotel transfers
- A personal coordinator throughout both stays
- Implant passport recording brand, model, dimensions and lot number for each implant
- Written treatment report and radiographs for your Canadian dentist
- English and French-speaking Canadian patient liaison available on request
7. The Journey, Step by Step
Trip 1 (7–10 days)
- Arrival — transfer to your 5-star hotel with your companion
- Assessment day — examination, CBCT, photographs, treatment plan confirmed
- Planning discussion — implant positions, bridge design, tooth shape and shade
- Surgery day — extractions and placement of four implants, under local anaesthesia or sedation; two to three hours per arch
- Temporary bridge fitted — same day or next day
- Review appointments — bite adjustment, healing check
- Discharge — instructions, medication, implant passport, radiographs
Between trips (3–6 months)
Osseointegration at home. Wearing the temporary. Interim monitoring in Canada.
Trip 2 (7–10 days)
- Review — radiograph confirming integration
- Impressions or digital scan
- Try-in — you approve shape, shade, length and bite before finalising
- Definitive bridge fitted
- Adjustment appointments over several days
- Final documentation for your Canadian dentist
Why the try-in matters enormously here
For a full arch, the try-in is not a formality. It is the only moment at which the appearance of your entire smile can still be changed. Look at yourself in natural daylight, not just under clinic lighting. Smile fully. Speak. Look from the side. Check how much tooth shows at rest and when smiling. Bring someone whose judgement you trust, or send photographs to someone at home. If something is not right — too white, too long, too uniform, not enough tooth showing — say so at this appointment. Changing it now is straightforward. Changing it after the definitive bridge is made means remaking it.
8. Recovery, Day by Day
Surgery day
You will have had multiple extractions and four implants placed, usually under local anaesthesia with or without sedation. Expect the anaesthetic to wear off over several hours, with oozing from the extraction sites for the first few hours. Take prescribed analgesia before the numbness fully fades. Ice on the outside of the cheeks in twenty-minute cycles. Cool liquids only. If your temporary bridge is fitted the same day, you will have teeth by evening — which most patients find remarkable given what has just happened.
Day 1
Swelling develops. This is the day patients underestimate: full-arch surgery involves extractions plus implant placement, and the swelling is greater than after a single implant. Facial swelling extending to the cheeks is normal and expected. Continue ice, soft cool foods, medication on schedule. Sleep propped up.
Days 2 to 3
Swelling peaks, often noticeably. Bruising may appear on the cheeks or under the jaw. Patients frequently look worse than they feel at this stage. This is the window for infection to declare itself. Increasing pain, fever, or a foul taste warrant contact with the clinic. Diet remains liquid to pureed. You have a bridge, but the sites beneath it are healing and should not be loaded.
Days 4 to 7
Marked improvement. Swelling recedes, discomfort becomes intermittent, most patients move to over-the-counter analgesia. Diet progresses to soft foods. Bite adjustment appointments happen in this window, and they matter — a temporary bridge that is high in one area concentrates force on one implant.
Days 7 to 10
Sutures removed if not self-dissolving. Final check before you fly. Most patients feel essentially functional, with residual tightness and mild tenderness.
Weeks 2 to 6
Gums remodel beneath the temporary bridge as the extraction sites heal. You may notice a small gap appearing between the bridge and the gum. This is normal — the gum is shrinking as it heals — and it is one reason the definitive bridge is made later, once tissue has settled. Some food may trap in that space. Cleaning technique matters; see section 12.
Months 2 to 6
Osseointegration proceeds silently. Maintain hygiene, treat the temporary gently, do not smoke.
After the definitive bridge
A period of adaptation lasting a few weeks: speech adjusts, the tongue learns the new contours, and chewing becomes progressively more efficient. Most patients report full adaptation within a month.
9. Managing Pain, Swelling and Eating
How painful is it?
Less than most patients expect given the extent of the surgery, but more than a single implant. Multiple extractions are the main contributor. Most patients describe a strong ache for two to three days, well managed with prescribed medication. Patients who have had teeth extracted before generally find it comparable to that experience.
What helps most
Ice for the first forty-eight hours. Sleeping propped up. Analgesia on schedule rather than on demand. Avoiding heat. Gentle salt water rinsing from day two as instructed.
Eating through the healing months
This is the practical challenge patients underestimate.
- Days 1 to 3: cool liquids and smooth purees. Soups, yoghurt, smoothies without a straw, mashed vegetables.
- Days 4 to 14: soft foods requiring minimal chewing. Scrambled eggs, fish, well-cooked pasta, soft cheese, banana.
- Weeks 2 to 6: progressively firmer soft foods. Minced meat, soft bread without crust, cooked vegetables.
- Months 2 to 6, with the temporary: most foods, but avoid hard and crunchy items — raw carrots, nuts, crusty bread, hard candy, ice, corn on the cob, ribs. Cut everything smaller than usual and distribute chewing across both sides.
- After the definitive bridge: most patients return to a normal diet. Zirconia is strong. Very hard items remain inadvisable, and using your teeth as tools remains a bad idea.
What if my temporary breaks?
It happens, usually from biting something too hard. It is not a medical emergency but it needs repair within a few days. This is exactly what your Canadian dentist arrangement is for. Contact the clinic as well so it is documented, and be honest about what you were eating — it may inform how the definitive bridge is designed.
10. Risks and Complications
Surgical risks
- Infection — uncommon with prophylaxis but requiring prompt treatment.
- Bleeding — usually minor; more oozing than bleeding after extractions.
- Swelling and bruising — expected, and more pronounced than after single implants.
- Nerve injury — in the lower jaw, altered sensation of the lip and chin. Usually temporary, occasionally permanent. CBCT planning is what minimises this risk.
- Sinus complications — in the upper jaw, though tilting is specifically designed to avoid the sinus.
- Failure of one implant to integrate — the most consequential specific risk in All-on-4. With only four implants supporting the arch, losing one matters more than losing one of six. Management may involve placing a replacement implant, or in some cases modifying the bridge design.
Ask about this at the quotation stage: if an implant fails to integrate, who bears the cost of replacement and of the additional trip? Get the answer in writing.
Prosthetic and long-term risks
- Fracture of the temporary bridge — relatively common, usually from hard food.
- Screw loosening — mechanical, straightforward to address if components are identifiable.
- Fracture of the definitive bridge — uncommon with zirconia, more likely in patients who grind.
- Peri-implantitis — inflammation with bone loss around implants, plaque-driven. The leading cause of late failure. See section 12.
- Speech changes — usually transient, occasionally requiring bridge modification.
- Food trapping beneath the bridge — manageable with correct cleaning technique, and influenced by bridge design.
What increases the risk of failure?
Smoking, above all. Then poor plaque control, uncontrolled diabetes, bruxism without a night guard, and skipping maintenance appointments.
Contraindications
Uncontrolled diabetes, active infection requiring treatment first, intravenous bisphosphonate therapy, recent head and neck radiotherapy, and incomplete jaw growth.
11. Warning Signs
Contact the clinic promptly if
- Pain increases rather than decreases after day three
- Swelling continues to grow beyond day four
- You develop a fever
- There is purulent discharge or a persistent foul taste
- Lip or chin numbness is not resolving
- The bridge feels loose or moves
- One area of the bridge suddenly feels high when you bite
Seek emergency care immediately if
- Facial swelling is spreading rapidly
- You have difficulty swallowing or breathing
- Swelling extends toward the eye or down the neck with fever
Spreading facial infection is a genuine emergency. Go to an emergency department.
If a problem arises after you get home
See your Canadian dentist, and contact the clinic in parallel. Bring your implant passport, radiographs and treatment report. A Canadian dentist facing a loose full-arch bridge of unknown system, with no records, is in a difficult position. The same dentist with documentation can usually help immediately.
12. Cleaning an All-on-4 Bridge: The Skill That Protects It
This section matters more than most patients expect, because the bridge does not come out and the space beneath it is where problems begin.
What is the challenge?
The bridge sits slightly above the gum, with a small space underneath. Food and plaque accumulate there. You cannot see it easily and you cannot reach it with a normal toothbrush. Plaque left in that space causes inflammation and, over time, peri-implantitis with bone loss around the implants. This is the leading cause of late All-on-4 failure, and it is almost entirely preventable.
What tools do I actually need?
- A water flosser is the single most useful item. Directed along the underside of the bridge, it flushes the space effectively. Most patients who succeed long term use one daily.
- Superfloss or bridge threaders — a thicker floss that can be passed under the bridge and drawn along it. Slower than a water flosser but very effective.
- Interdental brushes sized to fit under the bridge at the gum margin.
- A soft toothbrush for the bridge surfaces and the outer gum.
How long does it take?
Five to ten minutes daily once you have the technique. It feels awkward for the first week and then becomes routine. Ask for a hands-on demonstration before you leave the clinic. Being shown, with your own bridge in your own mouth, is worth far more than written instructions.
How often do I need professional cleaning?
Twice yearly minimum, more often if you have a history of gum disease. The hygienist should have appropriate instruments for implants. Some clinicians recommend removing the bridge periodically — annually or every few years — for thorough cleaning underneath. This is possible with screw-retained designs and is a reasonable question to ask about.
Does bridge design affect cleanability?
Substantially. A bridge with a smooth, convex underside is far easier to clean than one with concavities and ledges. This is a design decision made in the laboratory, and it directly affects your long-term outcome. It is a legitimate thing to ask about: “Is the underside designed for cleaning access?”
13. Bridge Materials for the Definitive Prosthesis
Monolithic zirconia
A single piece of zirconia, milled from a solid block. Very strong, resistant to fracture and wear, and the most common choice for full-arch work today. Aesthetics are good and improving as materials develop, though a highly layered ceramic can still surpass it for optical realism.
Titanium framework with ceramic or composite teeth
A metal bar supporting individual teeth. Repairable — a single tooth can be replaced without remaking the whole bridge, which is a genuine practical advantage. Bulkier than zirconia and the composite wears faster.
Acrylic on a titanium bar
Lower cost, lighter, and forgiving in patients with heavy bite forces because it absorbs some shock. Wears faster and stains more over time. Sometimes chosen deliberately for patients who grind heavily.
Which should I choose?
There is no single right answer, and this is a good question to ask your clinician to explain rather than to decide alone. Broadly: zirconia for strength and low maintenance; titanium with ceramic for repairability; acrylic for cost and shock absorption. Your bite force, whether you grind, your budget and your aesthetic priorities all bear on it. If you grind, raise it explicitly. It changes the recommendation.
14. Aesthetics: Getting the Appearance Right
Why is this harder than a single crown?
Because you are designing an entire smile from scratch. Tooth shape, size, colour, arrangement, how much shows at rest, how much shows when you smile, and how the bridge supports your lip — all are decisions rather than givens.
The most common aesthetic mistake
Teeth that are too white and too uniform. A full arch of identical, brilliantly white teeth reads as artificial immediately, particularly in someone over fifty. Natural teeth have slight irregularities, subtle variation in shade between teeth, and translucency at the edges. A skilled technician builds these in. Ask to see examples of the clinic’s full-arch work in natural light, and if everything looks like a row of white tiles, that tells you something about their aesthetic default.
How is the shade chosen?
Discuss it explicitly, and be honest about what you want. Some patients want conspicuously white teeth and that is a legitimate choice. Others want something that looks like their own teeth did at thirty. Both are achievable, but only if you say which. Bring a photograph of yourself smiling from years ago if you have one. It is more useful than any shade guide.
What about the opposing arch?
If you are treating one arch only, the new bridge must harmonise with your remaining natural teeth. This constrains the shade — a brilliant white upper bridge above natural lower teeth looks wrong. If you intend to whiten your natural teeth, do it before the bridge is made. Zirconia does not whiten.
Lip support and facial appearance
A full-arch bridge influences the fullness of your upper lip and the proportions of your lower face. Patients who have worn a denture for years may find that a well-designed bridge visibly improves their facial appearance. Conversely, a bridge that is too thin or set too far back can leave the lip unsupported. This is a planning consideration, and it is part of what the try-in appointment is for.
15. Living With All-on-4 Long Term
What can I eat?
After the definitive bridge, most patients report near-normal function. Bite force is substantially better than with a denture, though somewhat less than with natural teeth. Sensible limits: avoid very hard items, do not use your teeth as tools, and be cautious with things like hard nuts and ice.
Will I be able to taste and feel normally?
Taste is unaffected — an upper bridge, unlike a denture, does not cover the palate, which many patients find noticeably better. Sensation differs: implants have no nerve, so you will not feel pressure or temperature through the bridge as you would through natural teeth. Most patients adapt within weeks and stop noticing.
Will my speech change?
There is usually a brief adaptation period of days to a couple of weeks. If a persistent speech difficulty remains, the bridge can often be modified — raise it rather than accepting it.
How long will the bridge last?
The implants frequently last decades with proper maintenance. The bridge typically ten to fifteen years or longer depending on material, bite forces and hygiene. Plan for eventual bridge replacement as a normal maintenance cost. This is not a failure; it is the expected life cycle of a prosthesis.

What ongoing costs should I expect?
Professional cleaning twice yearly. Periodic radiographs. A night guard if you grind, replaced as it wears. Eventual bridge replacement. Occasional screw tightening or minor repair. These are modest annually but they are real, and they belong in your comparison with alternatives.
16. Aylan Clinic Across Canada: 50 Cities We Serve
The process begins identically wherever you live: a free online consultation with no need to travel beforehand. These are the fifty Canadian cities from which we most frequently receive enquiries, across English-speaking and French-speaking communities.
Ontario
Toronto and the Greater Toronto Area lead, including Mississauga, Brampton, Markham, Vaughan, Richmond Hill and Oshawa. Along the lake: Hamilton, Burlington, Oakville, St. Catharines and Niagara Falls. In the southwest: London, Kitchener, Waterloo, Cambridge, Guelph, Windsor and Barrie. Eastern Ontario: Ottawa and Kingston. Northern Ontario: Sudbury, Thunder Bay and Sault Ste. Marie — the first two with substantial francophone communities served in French.
Quebec
Montreal and surrounding municipalities including Laval, Longueuil and Brossard, together with Quebec City, Gatineau, Sherbrooke, Trois-Rivières, Saguenay, Drummondville, Saint-Jérôme and Lévis. All Quebec patients are served in French from first contact through the prosthetic phase.
British Columbia
Vancouver, Surrey, Burnaby and Richmond in the Lower Mainland, plus Victoria, Kelowna, Abbotsford, Nanaimo and Kamloops.
Alberta
Calgary and Edmonton, with additional patients from Red Deer and Lethbridge.
Prairies
Winnipeg, including the francophone community of Saint-Boniface, plus Saskatoon and Regina.
Atlantic Canada
Halifax, Moncton, Fredericton and Saint John — with Moncton and surrounding Acadian communities served in French — Charlottetown, and St. John’s.
Northern Canada
Whitehorse, and patients from the Northwest Territories and Nunavut.
A note for patients outside major centres
All-on-4 involves a temporary bridge worn for months, and temporaries occasionally break. If you live somewhere with limited dental access, plan this explicitly: identify who could repair a temporary, and consider timing your trips around periods when you have easier access to a dental office.
A note on domestic connections
Do not schedule a same-day domestic connection on your return from trip one. You will have had multiple extractions and four implants placed, and swelling peaks around day two to three. Build in an overnight stay near your international arrival airport.
17. The Honest Comparison
| What matters to you | Canada (private) | Turkey — Aylan Clinic |
|---|---|---|
| Clinical quality | Excellent | Equivalent, with high-volume experience |
| Cost | Very high for full-arch | Up to 60% less, all-inclusive |
| Coverage | Annual maximums make this largely out of pocket | Same, and foreign care often excluded |
| Number of trips | None | Two, spanning about a year |
| Temporary bridge repairs | Your own dentist | Requires a Canadian dentist arranged in advance |
| If an implant fails | Handled locally | Ask about the cost policy in writing first |
| Bridge replacement in 12 years | Your dentist has the records | Depends on your implant passport |
| Accommodation and meals | Your expense | 5-star hotel, full board included |
| Companion | Your expense | Free |
The bottom line: full-arch work is where the absolute dollar difference is largest, which is why this is among the most common reasons Canadians travel for dental care. There is no publicly funded alternative to weigh. What you must arrange deliberately is the continuity: a Canadian dentist for the healing months, and documentation good enough that any dentist can service the bridge in a decade.
18. Common Misconceptions
“One week and I’m finished.” No. One week gives you implants and a temporary bridge. The definitive bridge comes months later on a second trip. This is the most common misunderstanding about All-on-4 and the one most likely to cause resentment.
“Four implants can’t possibly hold a whole arch.” They can, and there is substantial published evidence behind the technique. The key is that they are well distributed along the arch — which is precisely why the posterior implants are tilted. Four bunched implants could not do it; four spread out can.
“All-on-4 means I never have to worry about my teeth again.” The opposite of the truth. The bridge cannot decay, but the implants can lose bone through peri-implantitis, and the space beneath the bridge requires daily attention. Maintenance is what determines whether this lasts fifteen years or five.
“It’s the best option for anyone missing teeth.” It is a full-arch solution. If you have healthy teeth in the arch, All-on-4 means removing them — a serious decision that is rarely appropriate. Individual implants or a bridge are usually better for partial tooth loss.
“All-on-4 is the same everywhere.” The name refers to a specific technique involving tilted posterior implants. Some clinics apply the label loosely to any four-implant arch. Ask specifically whether posterior implants will be tilted and why.
“It will feel exactly like natural teeth.” Very close for eating and speaking. Different in sensation, since implants have no nerve. Most patients stop noticing within weeks.
19. Mistakes to Avoid
- Believing one trip completes the treatment — it does not
- Accepting a plan with no CBCT imaging
- Having All-on-4 when you still have healthy teeth in the arch
- Not asking whether an implant-retained overdenture would serve you at lower cost
- Not asking what happens if an implant fails to integrate
- Leaving without your implant passport
- Not identifying a Canadian dentist for temporary repairs before travelling
- Biting hard foods on a temporary bridge
- Not attending the bite adjustment appointments
- Approving the definitive bridge at try-in without seeing it in natural light
- Choosing a shade that is too white and too uniform
- Whitening natural teeth after the bridge is made
- Not disclosing bruxism — it changes the material recommendation
- Skipping the hands-on cleaning demonstration before you leave
- Neglecting professional maintenance afterwards
- Continuing to smoke through the healing months
20. Illustrative Cases
A long-term lower denture wearer
A patient of sixty-eight who has worn a lower denture for twelve years and cannot keep it in place. Four implants with a fixed bridge transform her ability to eat. She describes it, as many do, as the best money she has spent. Worth noting: an implant-retained overdenture would also have improved her situation considerably at lower cost. She was offered both and chose fixed. That is how the conversation should go.
A failing upper arch
A patient of fifty-five with advanced periodontal disease, six remaining upper teeth all mobile, and recurrent infections. Individual implants are not viable in this bone with this disease history. All-on-4 with extraction of the remaining teeth is the appropriate solution, and the periodontal infection is resolved in the process.
A case where we recommend against it
A patient of forty-eight missing four upper teeth, with eight healthy, well-supported teeth remaining in the arch. He has read about All-on-4 and requests it. The honest answer is no. Removing eight healthy teeth to place four implants is not in his interest. Two or three individual implants, or an implant-supported bridge, address his actual problem. A clinic that agreed to his request would be doing him harm while taking more of his money.
A case where All-on-6 is recommended instead
A patient with soft upper bone, a heavy bite and a history of grinding. Four implants would be under considerable mechanical stress. Six implants distribute the load better. The additional cost is justified by the specific risk factors.
A case requiring staged treatment
A patient with active infection around several teeth. Extractions and infection control first, healing for several months, then implant placement. Three trips rather than two. This is slower and more expensive, and it is also correct. Placing implants into infected sites would compromise the whole investment.
21. Bruxism and All-on-4
Why does grinding matter so much here?
Because a full-arch bridge on four implants concentrates all your bite force onto four points, with no natural teeth to share the load and no cushioning ligaments. Grinding transmits that force repeatedly. Consequences over time: screw loosening, bridge fracture, and in severe cases bone stress around the implants.
What is done about it?
Three things. Material choice — some clinicians prefer acrylic or composite for heavy grinders because it absorbs shock rather than transmitting it. Additional implants — All-on-6 rather than All-on-4. And a custom night guard, worn every night without exception.
How do I know if I grind?
Waking with jaw ache or headaches, a partner who has heard it, previously worn or chipped teeth, or a dentist who has pointed out the wear pattern. Disclose it at planning. It genuinely changes the recommendation, and it is far cheaper to plan for than to repair.

22. Smoking and All-on-4
Why is it particularly relevant here?
Because you are asking four implants to integrate simultaneously and then to carry an entire arch. Nicotine impairs the bone healing that this depends on, and increases the risk of peri-implantitis afterwards. With only four implants, losing one has more consequence than losing one of six or one of twelve individual implants.
For how long should I stop?
Ideally permanently. At minimum from two weeks before surgery until integration is complete, three to six months later.
Practical support
Canadian provincial quitlines are free. Pharmacists can advise on nicotine replacement and prescription options. Combining behavioural and pharmacological support roughly doubles success rates. Vaping carries the same nicotine-related concern. Discuss it rather than assuming it is neutral. Be honest with the team about where you actually are. A plan can be adjusted for a patient who still smokes; it cannot be adjusted for information withheld.
23. Choosing a Clinic: The Questions That Discriminate
| Question to ask | Reassuring answer | Concerning answer |
|---|---|---|
| “Will the posterior implants be tilted, and why?” | An explanation referencing your sinus or nerve anatomy from the CBCT. | Not knowing what the question means. |
| “Will I have a CBCT before the plan is finalised?” | “Yes, on assessment day.” | “The panoramic is sufficient.” |
| “Is the bridge I leave with temporary or definitive?” | A clear two-trip explanation. | Ambiguity, or “you’ll go home with your new teeth.” |
| “Which implant brand, and is it distributed in Canada?” | A specific named system. | “A premium European brand.” |
| “What happens if one implant fails to integrate?” | A written policy covering the replacement and, ideally, some contribution to travel. | “That doesn’t happen.” |
| “Would an implant-retained overdenture achieve enough for me, at lower cost?” | A genuine discussion of the trade-offs. | Immediate dismissal. |
| “Is the underside of the bridge designed for cleaning access?” | Yes, with an explanation of the contour. | Puzzlement. |
| “Will I get a hands-on cleaning demonstration before I leave?” | Yes, with the hygienist. | “We’ll give you a leaflet.” |
| “Can I see full-arch cases at one year or later, in natural light?” | A range of cases, including patients over sixty with natural-looking shades. | Only bright white, uniform smiles, all photographed at delivery. |
24. Warranties and What Happens Later
What is typically guaranteed?
Implant manufacturers generally guarantee the fixture against defect, often for life. Clinics typically guarantee the prosthetic work for a defined period.
What is usually excluded?
Failure attributable to smoking, poor hygiene, missed maintenance, trauma, or untreated bruxism. Normal wear of the bridge is also excluded.
The questions that matter for a patient treated abroad
“If the bridge fractures in three years, who pays for the remake, and who pays for the travel?” “Does the warranty require maintenance appointments, and must they be with you?” “If a screw loosens, can a Canadian dentist address it, or does it require a return trip?” That last question is worth asking specifically. Minor prosthetic maintenance is far easier if your components are widely available and your documentation is complete. Get the answers in writing.
25. Understanding the Full Cost
What the quote should cover
Consultation, CBCT, extractions, four implants per arch, abutments, temporary bridge, definitive bridge, hotel with full board, transfers, coordination, implant passport and documentation.
What is not in the quote
Flights for two trips, travel insurance, interim visits and temporary repairs in Canada, ongoing professional maintenance, a night guard if you grind, and eventual bridge replacement in ten to fifteen years.
Building an honest total
Add two sets of flights, your Canadian interim care, and the maintenance you will need regardless. Compare that figure — not the headline price — against a Canadian quote. See our pricing in Turkey page for a fuller overview.
Why the cheapest quote is rarely best value
On full-arch work, savings come from: no CBCT, an unidentified implant system, a temporary presented as definitive, a lower-grade bridge material, no try-in stage, and no cleaning instruction. Every one of those either transfers cost to you later or reduces how long the result lasts.
26. Second Opinions
Worth getting?
Yes, and particularly on three questions: whether you need full-arch treatment at all, whether four or six implants is right for you, and whether an overdenture would serve you adequately. These three questions account for most of the variation between treatment plans, and all three have major cost implications.
How does Aylan Clinic respond?
We encourage it. On full-arch work especially, a patient who understands why a particular plan was proposed is a better-informed patient and a more satisfied one.
27. Glossary
- All-on-4 — full-arch fixed bridge on four implants, two of them tilted
- Tilted implant — angled placement to engage more bone and avoid sinus or nerve
- Immediate loading — fitting a temporary bridge at the time of placement
- Temporary bridge — fixed acrylic prosthesis worn during osseointegration
- Definitive bridge — the final prosthesis, fitted on the second trip
- Osseointegration — bone growing onto the implant surface; three to six months
- CBCT — cone beam CT; the 3D imaging that makes tilted placement safe
- Monolithic zirconia — single-material bridge, maximum strength
- Peri-implantitis — inflammation with bone loss around implants
- Screw-retained — bridge fixed with screws, removable for maintenance
- Implant passport — record of brand, model, dimensions and lot number
- Overdenture — removable denture clipping onto implants; a lower-cost alternative
- Try-in — appointment to approve appearance before the bridge is finalised
28. How Canadians Actually Search for This
- “All on 4 dental implants Turkey cost” — the search that starts most enquiries.
- “All on 4 cost Canada” — the comparison point. Full-arch work is where the dollar gap is largest.
- “Teeth in a day” — describes immediate loading with a temporary bridge, not a finished treatment.
- “All on 4 vs All on 6” — depends on bone quality, bite force and grinding. Both guides available.
- “Full mouth dental implants abroad reviews” — read them, but weigh process detail over photographs.
- “How long does All on 4 last” — implants often decades; the bridge ten to fifteen years or more.
- “All on 4 problems” — most commonly temporary fractures, screw loosening, food trapping and peri-implantitis.
- “Cleaning under All on 4 bridge” — a water flosser plus superfloss, daily. The skill that protects the investment.
- “All on 4 too white” — a real and frequent regret. Address it at the try-in.
- “Implant supported denture vs All on 4” — the cost-conscious comparison most patients should make and often do not.
- “All on 4 gap under bridge” — normal as gums shrink after extractions; one reason the definitive bridge comes later.
- “Do I have to remove all my teeth for All on 4” — in the treated arch, yes. Which is why it is wrong for a partially intact arch.
- “All on 4 and grinding teeth” — changes both the material choice and the number of implants recommended.
- “Speaking with All on 4” — a short adaptation period is normal; persistent difficulty can usually be modified.
In Summary: All-on-4 in Turkey With Aylan Clinic
All-on-4 in Turkey with Aylan Clinic combines experienced oral surgeons and prosthodontists, mandatory CBCT-based planning of tilted implant placement, a fixed temporary bridge so you are never without teeth, a try-in stage before the definitive bridge is finalised, and comprehensive support — 5-star hotel, free companion — for up to 60% less than Canadian private prices.
Five things determine whether this goes well: understand the two-trip timeline, you leave trip one with a temporary and the definitive bridge comes months later; confirm this is the right treatment, and if you have healthy teeth in the arch it probably is not, so ask about individual implants or an overdenture; insist on CBCT, since tilted placement without 3D imaging is guesswork about the sinus and nerve; learn to clean under the bridge, with a hands-on demonstration before you leave, because this is what makes it last; and leave with your implant passport, having arranged a Canadian dentist before your first trip.
To go further, read the full All-on-4 in Turkey procedure page, explore our wider dental care in Turkey section, or see pricing in Turkey for a personalised assessment.

