Sleeve gastrectomy at Aylan Clinic gives international patients access to the most widely performed bariatric procedure in the world, with a full pre-operative workup including endoscopy, a ten-day monitored stay, and a structured follow-up plan, for up to 60% less than private prices at home. The sleeve is the most commonly performed weight-loss operation globally because it does a great deal with a relatively straightforward technique: most patients lose a substantial proportion of their excess weight, and the improvement in conditions like type 2 diabetes, sleep apnoea, hypertension and joint pain is frequently the change patients describe as mattering most.
This guide complements our Gastric Sleeve in Turkey procedure page and sits within our bariatric surgery in Turkey section. Two things distinguish a serious bariatric programme from a cheap one, and we build both into every plan: a pre-operative endoscopy, because what it finds occasionally changes the operation recommended and it is better known beforehand; and a follow-up and supplementation plan arranged before you travel, because the sleeve works for decades when the follow-up is in place. Section 12 explains exactly how to set that up. At any time you can consult our pricing in Turkey page.
1. Understanding sleeve gastrectomy
What the operation does
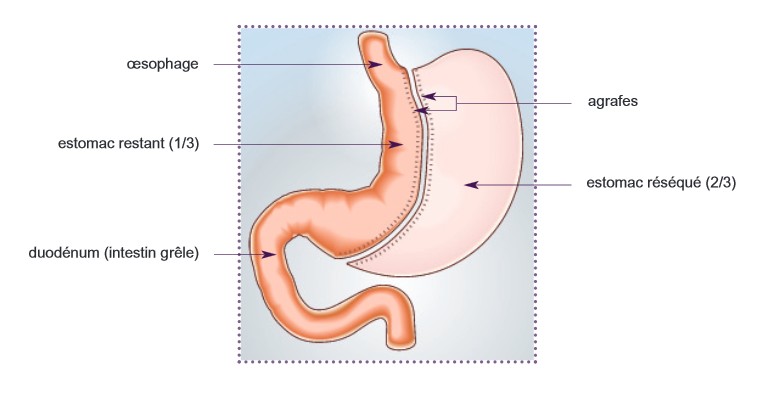
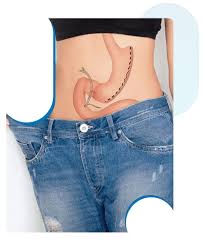
Approximately three-quarters of the stomach is removed, leaving a narrow vertical tube — the “sleeve” — roughly the shape and volume of a banana. It is performed laparoscopically, through four or five small incisions, and takes around an hour to ninety minutes.
Why it produces weight loss
Two mechanisms, and the second matters more than most patients expect.
- Restriction. The stomach holds far less, so meals are much smaller and you feel full quickly.
- Hormonal change. The portion of stomach removed is the main site producing ghrelin, the hormone that drives hunger. Most patients report a marked reduction in appetite — not simply an inability to eat, but a genuine reduction in wanting to.
That hormonal effect is why the sleeve outperforms purely restrictive procedures, and it is what patients most frequently describe as the surprising part: food stops occupying their thoughts.
What it does not change
Absorption. The intestine is untouched, so the sleeve is restrictive rather than malabsorptive — which means fewer nutritional consequences than a bypass or a SADI-S, and simpler supplementation.
Is it reversible?
No. The portion of stomach removed is removed permanently. This is worth understanding clearly rather than as a warning: it is a definitive decision, and it is one of the reasons the pre-operative workup and the follow-up plan matter. Patients who go in fully informed are the ones who do well, and satisfaction with the sleeve is high.
What the results look like
Most patients lose a substantial proportion of their excess weight over twelve to eighteen months, with the fastest loss in the first six months. The figures vary between individuals, and your surgeon will give you a realistic expectation for your starting point rather than a promise. What is consistent is the pattern: rapid early loss, continued loss through the first year, then stabilisation.
The health changes patients notice
Frequently more significant to them than the weight itself.
- Type 2 diabetes improves substantially in a large proportion of patients, and a meaningful number reduce or stop medication — sometimes within weeks, before much weight has been lost, because of the hormonal changes.
- Sleep apnoea improves markedly in most patients, and many stop using CPAP.
- Blood pressure and cholesterol improve in the majority.
- Joint pain eases, which for many patients is what finally makes exercise possible.
- Mobility, energy and sleep quality — the changes patients mention first when asked what is different.
2. Are you a candidate?
The usual criteria
Bariatric surgery is generally considered for patients with a BMI of 40 or above, or a BMI of 35 or above with an associated condition such as type 2 diabetes, sleep apnoea, hypertension or significant joint disease. Some programmes consider patients with a BMI of 30 to 35 where type 2 diabetes is poorly controlled. Your assessment establishes where you sit, and we will tell you honestly at the online consultation stage whether the sleeve is the right procedure for you or whether another would serve you better.
What else matters
- A history of attempted weight loss, which most patients have in abundance.
- Understanding that this is a tool rather than a cure. The sleeve makes sustained change possible; it does not make it automatic. Patients who understand that do well.
- Willingness to take supplements and attend follow-up for life. This is the single strongest predictor of a good long-term outcome, and it is straightforward once set up.
- Stable mental health, and support around you.
Where another procedure may suit you better
Worth knowing, because it is a genuine conversation rather than a formality.
- Significant reflux — the sleeve can worsen reflux, and where reflux is already established a bypass frequently serves patients better. This is one of the main things the pre-operative endoscopy establishes.
- A very high BMI — where BMI is extremely high, or where diabetes is severe and long-standing, a bypass or a SADI-S may produce more substantial and durable results.
- A previous gastric band — conversion has its own considerations, covered in our band guide.
We will set this out at your consultation. Recommending the procedure that suits you rather than the one you enquired about is what a proper assessment involves.
3. Sleeve, bypass, or something else?
Sleeve gastrectomy
Restrictive with a strong hormonal effect. Technically straightforward, no intestinal rerouting, simpler supplementation, and no risk of the internal hernia that a bypass can produce years later. Best for: the majority of patients, and particularly those without significant reflux.
Gastric bypass
Restrictive and moderately malabsorptive, with a stronger effect on type 2 diabetes and a beneficial effect on reflux. More complex, with lifelong supplementation requirements that are more demanding, and anti-inflammatory medication is avoided permanently. Best for: patients with significant reflux, severe or long-standing diabetes, or a very high BMI. Covered in our bypass guide.
SADI-S
The most effective procedure for weight loss and diabetes, and the most malabsorptive — which means the most demanding lifelong follow-up and supplementation of any bariatric operation. Best for: very high BMI, severe diabetes, or as a revision after a sleeve. It requires the most committed follow-up, and our guide sets that out in detail.
Gastric balloon
Temporary, non-surgical, and reversible. Placed endoscopically and removed after six to twelve months. Best for: patients wanting a temporary tool, those not ready for surgery, or as a bridge to reduce weight before another procedure.
Gastric band
Largely superseded. Our band guide covers removal and conversion, which is what most band enquiries now concern.
How the decision is made
From your BMI, your associated conditions, your endoscopy findings — particularly regarding reflux — your previous surgery, and your own priorities. Your assessment sets out which procedures suit you and why. Where more than one is reasonable, you will have the trade-offs explained and the choice is yours.
4. Why international patients choose Turkey — and the route home
| Factor | At home | Turkey — Aylan Clinic |
|---|---|---|
| Cost | Covered in the public system where you qualify | At your expense, well below private prices |
| Wait time | Frequently years | Weeks |
| Accommodation | Not applicable | 5-star hotel, full board included |
| Companion | Not applicable | Free, accommodated and fed |
| Length of stay | Local | 10 days with daily monitoring |
| Dietitian programme | Standard in public programmes | Included, with a written plan |
The public route at home
Worth stating clearly: bariatric surgery is available in the public system in most regions for patients who meet the criteria, at no cost. The obstacle is waiting time, and in many places it is measured in years — frequently two to five from referral to surgery, including a mandatory pre-operative programme. We suggest asking your family doctor about a referral and the realistic wait. If it is manageable, the public route offers something we cannot: the whole team in one place, permanently, including the dietitian and the follow-up.
If the wait is not liveable for you — and for a patient with poorly controlled diabetes or severe sleep apnoea, several years is a genuine health consideration rather than an inconvenience — then this is a reasonable alternative, chosen knowingly. That is why most of our international bariatric patients arrive having already been on a waiting list.
What we do differently from a short-stay programme
Three things, and they are the reason our stay is ten days rather than five.
- A full pre-operative workup including endoscopy, which occasionally changes the recommended procedure.
- Ten days of monitored recovery, which covers the window in which the one serious early complication of a sleeve would declare itself. Section 13 explains why that matters more than any other logistical decision.
- A written follow-up and supplementation plan designed for a patient who lives far away, plus help in setting it up before you travel.
5. Assessment: what a full workup includes
The online consultation
You send your details and photographs, and your surgeon reviews them. You receive an initial plan and quote, including whether the sleeve is the right procedure for you. What to send: your height, weight and BMI, a list of your medical conditions and all medications, your weight history, details of any previous abdominal surgery, and a note of whether you have reflux or heartburn.
On-site assessment
- Upper gastrointestinal endoscopy — the examination that matters most, and section 6 explains why it is not optional.
- Blood work, including a full nutritional panel: iron, ferritin, B12, folate, vitamin D, calcium, and thyroid function. This establishes your baseline, and a proportion of patients are already deficient before surgery.
- Abdominal ultrasound, which checks the liver and looks for gallstones — relevant because rapid weight loss increases the chance of gallstones becoming symptomatic.
- Cardiac and respiratory assessment, proportionate to your BMI and conditions.
- Sleep apnoea screening, and where it is suspected, assessment. This matters for the anaesthetic, and a substantial proportion of bariatric patients have undiagnosed sleep apnoea.
- Anaesthetic review, which for a higher BMI is more thorough than usual.
- Dietitian consultation, which sets your eating progression and your supplementation plan.
Why the nutritional baseline matters
Because deficiencies identified before surgery can be corrected before surgery, and because knowing your starting values makes your follow-up bloodwork interpretable. A patient whose ferritin was already low before a sleeve needs different supplementation from one whose was normal. That is the kind of thing a full workup establishes.
6. The pre-operative endoscopy
What it involves
A short examination of the oesophagus, stomach and first part of the small intestine, performed under sedation. It takes ten to fifteen minutes and most patients remember nothing of it.
What it looks for
- Reflux and oesophageal inflammation. The single most important finding. A sleeve can worsen reflux, and where significant reflux or inflammation is present, a bypass frequently serves the patient better. This is why the endoscopy occasionally changes the recommended procedure — and it is far better to know before the operation than after.
- Hiatus hernia, which is common, which contributes to reflux, and which can be repaired at the same time as the sleeve.
- Ulcers or gastritis, which are treated before surgery.
- Helicobacter pylori, which is looked for and treated if present.
- Anything else — the stomach being removed is examined first, which is straightforward good practice.
Why we include it as standard
Because it changes management in a meaningful proportion of patients, and because operating on a stomach nobody has looked at is planning without information. Ask any bariatric programme whether endoscopy is included. A programme that does not perform it before a sleeve is omitting the examination that most often alters the plan.
If it finds something
Most findings are minor and treated straightforwardly — a course of medication before surgery, or a hiatus hernia repaired at the same operation. Where reflux is significant, your surgeon will discuss whether a bypass would serve you better. That is a conversation worth having, and it is the reason the examination exists.
7. Preparing for surgery
The pre-operative diet
You will be given a diet to follow for two to four weeks before surgery, depending on your BMI. Its purpose is specific and worth understanding: it reduces the size of the liver. A larger liver sits over the upper stomach and makes laparoscopic access more difficult, so shrinking it makes the operation safer and technically easier. Patients who follow it properly have shorter, more straightforward operations. It is one of the few things entirely within your control before surgery, and it genuinely matters. Your dietitian provides the plan, and locally available foods are used.
Stopping smoking
Genuinely important before abdominal surgery — it affects healing and increases respiratory complications after a general anaesthetic. Stopping at least four weeks before makes a measurable difference. Free quitlines exist in most regions, your pharmacist can advise on nicotine replacement, and combining behavioural with pharmacological support roughly doubles success rates. Tell us honestly where you are; the plan can be adapted.
Medications
Bring a complete list, including supplements. Some are stopped before surgery. Disclose specifically: blood thinners, diabetes medications — which frequently need adjusting as your intake changes — hormonal contraception, and anything for reflux.
What to arrange at home before you travel
Three things, and section 12 covers the first two in detail.
- A follow-up plan with your family doctor. One conversation, before you go.
- Your supplements, purchased and ready.
- Soft food for the first weeks home, prepared or arranged.
8. Your trip, day by day
Ten days, and this is deliberate rather than generous.
Day 1 — Arrival
Your driver meets you at the airport and takes you to your hotel with your companion. Nothing clinical today.
Day 2 — Assessment
The full workup: endoscopy under sedation, blood work, abdominal ultrasound, cardiac and respiratory assessment, and anaesthetic review. Then your consultation with the surgeon, and your dietitian appointment covering the eating progression and supplementation. By the end of the day your plan is confirmed — including whether the endoscopy findings suggest a different procedure would serve you better.
Day 3 — Surgery
The operation under general anaesthesia, laparoscopically, around one to one and a half hours. You wake in your room. You will be helped up to walk the same day, which is the single most effective measure against blood clots and against chest complications. Nothing by mouth initially, then sips of water.
Days 4 to 5 — In hospital
Monitoring, with your blood tests and observations checked. Progression from water to clear liquids. Mobilisation increases — you will be walking the corridor several times a day, which feels like a lot and matters a great deal. Most patients are surprised by how little pain there is. The dominant sensations are pressure in the shoulder from the gas used during laparoscopy, and a feeling of fullness after very small volumes.
Day 6 — Transfer to hotel
Discharge to your hotel, with daily nursing visits from here. Progression to full liquids under your dietitian’s plan.
Days 7 to 9 — Monitored recovery
Daily nursing visits, and your dietitian available. This is the window that matters, and section 13 explains why. Most patients feel substantially better each day. Short walks around the hotel and nearby become comfortable, and a number of patients manage a gentle outing by day eight or nine.
Day 10 — Final review and departure
Your surgeon reviews you, and you receive your documentation: operative report, your endoscopy and pathology results, your blood work baseline, your written dietary progression, your supplementation prescription, and a follow-up schedule addressed to your own doctor. Then your transfer to the airport.
If you would rather stay longer
Some patients extend by two or three days, particularly those facing a long journey home. There is no clinical requirement beyond ten days in an uncomplicated recovery, and the extra days are comfortable.
9. Recovery, week by week
Week 1 — in Turkey
Covered above. Liquids, walking, daily monitoring, and a steady improvement.
Week 2
Home. Fatigue is the dominant feature, and it is more pronounced than patients expect — you are on a very low calorie intake while recovering from surgery. Pureed foods begin according to your dietitian’s plan. Walking daily, increasing gradually. Most patients return to desk work at two to three weeks.
Weeks 3 to 4
Energy improves noticeably. Soft foods progress. Weight loss is rapid in this period and visible week to week. Physical work: four to six weeks. No heavy lifting for six weeks, to protect the incision sites.
Weeks 5 to 8
Solid foods reintroduced gradually. Portion sizes remain very small and this is normal. Exercise progresses: walking throughout, light cardio from four weeks, and resistance work from six to eight.

Months 3 to 6
The period of fastest weight loss. Most patients feel substantially better in energy, mobility and sleep. Your first follow-up bloodwork is due in this window — section 12 sets out the schedule. Hair thinning is common around months three to five and it resolves. It is related to the rapid weight loss and to protein intake, and it is temporary. Patients who are warned about it find it much less alarming.
Months 6 to 18
Weight loss continues at a slower rate and then stabilises. Portion capacity increases somewhat, which is expected. This is the period in which the habits you build determine the long-term result, and it is why the dietitian relationship matters.
Beyond 18 months
Your weight stabilises. Follow-up continues annually — bloodwork, supplementation review, and a check that everything is holding.
10. Eating after a sleeve
Your dietitian provides a written plan, in stages. This is the outline, and yours will be specific to you.
| Stage | Timing | What it involves |
|---|---|---|
| Stage 1 — clear liquids | The first days | Water, clear broth, sugar-free jelly, diluted juice. Sipping rather than drinking. A very small volume fills you. |
| Stage 2 — full liquids | Roughly days 5 to 14 | Thin soups, milk, unsweetened yoghurt drinks, protein drinks. Protein becomes the priority from here, and it stays the priority permanently. Your plan sets a target and tells you how to reach it. |
| Stage 3 — pureed | Roughly weeks 2 to 4 | Smooth textures — pureed soups, blended chicken or fish, cottage cheese, mashed vegetables. |
| Stage 4 — soft | Roughly weeks 4 to 8 | Flaked fish, minced meat, scrambled eggs, soft cooked vegetables, well-cooked pasta. |
| Stage 5 — regular | From around week 8, gradually | Most foods return, in small portions. |
The habits that matter permanently
- Protein first, at every meal.
- Small portions, eaten slowly. Twenty to thirty minutes for a meal.
- Chew thoroughly.
- Do not drink with meals — fluids fill the sleeve and displace food. Thirty minutes before or after.
- Fluids between meals, and a target volume across the day. Dehydration is the most common reason patients feel unwell in the first weeks, and it is entirely avoidable.
- Avoid fizzy drinks, which are uncomfortable.
What patients find harder than expected
- Drinking enough, because you can no longer drink a glass of water in one go. It takes deliberate effort in the first weeks.
- Eating slowly, which is a habit rather than a rule and takes practice.
- The social side of eating, since your portions are conspicuously small. Most patients find this settles within a few months.
What patients find easier than expected
Not being hungry. The hormonal effect of the sleeve means most patients simply do not want food the way they did, and they describe this as the part that makes everything else possible.
11. Vitamins and supplementation
Why supplements are needed
A smaller stomach means less food, less stomach acid, and less of the intrinsic factor needed to absorb vitamin B12. The sleeve is restrictive rather than malabsorptive, so its supplementation requirements are simpler than a bypass or a SADI-S — but they are lifelong.
What is typically required
- A complete bariatric multivitamin, formulated for post-surgical needs rather than a standard supermarket multivitamin.
- Vitamin B12, which many patients take sublingually or by injection.
- Iron, particularly in menstruating women.
- Calcium with vitamin D.
- Protein supplementation in the early months, until food intake covers your target.
Your prescription is specific to your baseline blood work, which is why the pre-operative panel matters.
Where to buy them
Bariatric-specific multivitamins are available from pharmacies and specialist suppliers. Your plan names the formulations and the doses, so you can source equivalents locally. Buy your first three months before you travel if you can. It removes one thing from a week when you will be tired.
Taking them for life
This is the single most important thing you will do for your long-term health after a sleeve, and it is genuinely straightforward once it becomes routine. The consequences of not taking them appear years later and are entirely preventable. Patients who set up a routine in the first month — a pill organiser, a phone reminder — do not find it burdensome.
Bloodwork schedule
Typically at three months, six months, twelve months, then annually for life. Your plan sets the schedule and the panel, addressed to your own doctor.
12. Setting up your follow-up at home
This is the section that most determines whether your sleeve works well for twenty years, and it takes one conversation before you travel.
What follow-up involves
Not much, and that is worth saying. Bloodwork at three, six and twelve months, then annually. A supplementation review. And someone to ask if you have a question. That is it. It is not a demanding commitment.
Who provides it
Your family doctor, in most cases. The bloodwork panel is standard, the supplements are over-the-counter or simply prescribed, and the interpretation is straightforward with the schedule we provide.
How to arrange it
Have the conversation before you travel, and it is a simple one: “I’m having a sleeve gastrectomy. I’ll come back with an operative report, my baseline bloodwork and a follow-up schedule. Would you be able to order the bloodwork at three, six and twelve months and then annually, and review my supplements?” Most family doctors say yes without hesitation. It is routine work, the schedule is provided, and they are generally glad the plan exists.
If your doctor is hesitant
Some are cautious about surgery they did not arrange, which is a reasonable professional position rather than obstruction. What helps: approaching them beforehand rather than afterwards, being clear that you are asking for bloodwork and supplement review rather than for them to take over the surgical case, and bringing the written schedule. If they decline, alternatives exist — a walk-in clinic can order bloodwork, and some regions have bariatric follow-up clinics that accept patients who had surgery elsewhere. Ask us and we will help you work out the options where you live.
Why we insist on this
Because the sleeve is a good operation with a good long-term record in patients whose follow-up is in place. The difference between those two groups appears at year five and year ten, not at week six. Arranging it is easy. Not arranging it is the one avoidable mistake in an otherwise straightforward pathway, and we would rather help you set it up than watch you skip it.
13. The flight home: why ten days
The interval
Ten days minimum, and this is the most important logistical decision in your whole plan.
Why
The one serious early complication of a sleeve is a staple line leak, and its characteristic window is days five to ten after surgery. It is uncommon. When it occurs, it needs recognising quickly and managing in a hospital with a bariatric team — which is exactly what you have here and exactly what you do not have on a long-haul flight or in an emergency department that has never seen you. Staying through that window is what makes travelling for a sleeve safe. A programme that sends patients home on day five has moved the risk from itself to the patient.
What we watch for
Daily observations, blood tests, and clinical review. The signs are recognisable to a team that sees them: a rising heart rate, increasing abdominal pain, fever, or feeling unexpectedly unwell rather than progressively better. Your nursing visits are checking for exactly this, and by day ten the window has passed.
Ask this of any programme
“How many days do I stay, and why that number?” The answer tells you a great deal. A specific answer referencing the leak window is what you want. “Five days” without explanation is a red flag on a bariatric procedure in a way it would not be on a cosmetic one.
Making the flight comfortable
- Book an aisle seat. Get up and walk every hour — thrombotic risk after abdominal surgery in a patient who has recently been immobile warrants real attention.
- Wear graduated compression stockings, and continue any prescribed anticoagulation exactly as directed.
- Bring your fluids and sip constantly. Dehydration is the main practical issue on the flight, and airline cups are the wrong shape for someone who has to sip.
- Bring your own food — small portions of something on your current stage. Airline meals will not suit you.
- Do not book a same-day domestic connection. Build in an overnight stay near your arrival airport.
14. The longer term
Weight loss and stabilisation
Rapid in the first six months, continuing more slowly through the first year, then stabilising. Some regain after the first two years is common and is not a failure — it is the pattern seen in every long-term series. Where it happens, it is usually modest, and the habits and follow-up you have in place determine how modest.
What helps it hold
Protein at every meal. Eating slowly and stopping when full. Regular activity, which becomes genuinely possible as weight comes off. Attending your annual review. And not drinking calories, which is the most common route back. Your dietitian covers all of this, and the plan you take home is specific rather than general.

Alcohol
Worth knowing about. After a sleeve, alcohol is absorbed faster and reaches a higher peak — you will feel effects from far less than before. There is also a documented increase in problematic alcohol use after bariatric surgery in a proportion of patients. It is worth being aware of, and worth mentioning to us if alcohol has been an issue for you.
Pregnancy
Entirely possible after a sleeve, and many patients have healthy pregnancies. Fertility frequently improves as weight comes off, which occasionally surprises patients. Waiting twelve to eighteen months is recommended, so that your weight has stabilised and your nutrition is settled — pregnancy during rapid weight loss is not ideal for either of you. Two practical points: contraception needs to be reliable in that window, and your nutrition and supplementation need reviewing before and during pregnancy. Tell your obstetrician you have had a sleeve.
Gallstones
Rapid weight loss increases the chance of gallstones becoming symptomatic. Your ultrasound checks for existing stones, and where they are present the plan may include addressing them.
Reflux
The sleeve can cause or worsen reflux in a proportion of patients. Where it occurs it is usually manageable with medication; occasionally it leads to conversion to a bypass. This is the main reason the pre-operative endoscopy matters, and it is why patients with existing reflux are frequently better served by a bypass from the outset.
Skin
Substantial weight loss leaves loose skin, to a degree that depends on how much you lose, your age and your skin quality. Body contouring surgery is an option once your weight has been stable for at least six months, and typically twelve to eighteen months after your sleeve. A number of our patients return for it, and it is worth knowing the option exists rather than discovering it later.
15. Aylan Clinic across your region
Aylan Clinic works with patients from every region. Wherever you live, the process begins the same way: a free online consultation, with your details sent from home and no need to travel before your dates are confirmed. For this procedure the return journey matters, so we plan it carefully with you.
Wherever you are travelling from, a direct flight to Istanbul is a genuine advantage for a procedure where the return journey matters, and where a direct option is not available we plan the connection carefully. Journeys that involve a domestic connection mean a second flight on the same day, so an overnight stay near your arrival airport on the return is strongly recommended. Given the amount of sitting involved on longer journeys, some patients extend to twelve or thirteen days, and we generally suggest it — the additional recovery before a long flight is worthwhile.
How we handle the logistics
Whichever city you are travelling from, your coordinator arranges airport transfers at both ends in Istanbul, confirms your hotel before you depart, and builds your schedule around your arrival time. Four recommendations for every patient: schedule your assessment for the day after you land — your endoscopy is better done rested; book a changeable return fare where you can, since your departure date is confirmed by your surgeon; avoid a same-day domestic connection on your return — this matters more here than for any other procedure in our series; and arrange your follow-up before you travel, which section 12 covers. If you are unsure how to structure your travel from your city, ask before booking. We have arranged bariatric trips from most parts of the world.
16. What the package includes
- Free online consultation with a plan and quote, including whether the sleeve is the right procedure for you
- Full on-site workup: upper GI endoscopy, complete nutritional blood panel, abdominal ultrasound, cardiac and respiratory assessment, sleep apnoea screening
- Anaesthetic review proportionate to your BMI and conditions
- Dietitian consultation with your written eating progression
- Surgeon consultation and your confirmed plan
- The procedure, general anaesthesia, and hospitalisation
- Hiatus hernia repair where indicated and found at endoscopy
- Three to four nights in hospital with continuous monitoring
- Daily nursing visits for the remainder of your ten-day stay
- Dietitian available throughout your stay
- Medication, including anticoagulation as prescribed
- Your supplementation prescription, specific to your baseline bloodwork
- Final surgical review before departure
- Complete documentation: operative report, endoscopy and pathology results, baseline bloodwork, written dietary progression, supplementation plan, and a follow-up schedule addressed to your own doctor
- Help identifying and arranging your follow-up at home before you travel
- 5-star hotel accommodation, full board adapted to your dietary stage
- A companion at no extra cost, accommodated and fed in the same room
- Airport–clinic–hotel transfers
- A personal coordinator from arrival to departure
- English and French-speaking patient liaison available on request
The clinical team
- Bariatric surgeon — laparoscopic sleeve gastrectomy and revision surgery
- Gastroenterologist — pre-operative endoscopy
- Anaesthetist — assessment and monitoring, with bariatric anaesthesia experience
- Bariatric dietitian — your eating progression and supplementation plan
- Internal medicine input — where diabetes or other conditions need managing around surgery
- Dedicated nurse — daily post-operative care throughout your stay
17. Results by patient profile
Type 2 diabetes as the driver
A patient in his forties with a BMI of 41 and type 2 diabetes on two medications, who had been on a public waiting list for two years. His endoscopy was clear and the sleeve proceeded. His diabetes medication was reduced within six weeks — before he had lost much weight — and stopped by month five. He describes the diabetes change as the reason he did it, ahead of the weight.
Where the endoscopy changed the plan
A patient who enquired about a sleeve and whose endoscopy showed significant reflux with oesophageal inflammation. Her surgeon recommended a bypass instead, explaining that a sleeve would likely worsen the reflux. She took a week to consider it and proceeded with the bypass. This is what the endoscopy is for, and it happens often enough to matter.
Sleep apnoea resolved
A patient with a BMI of 44 who had used CPAP for six years. At eight months post-sleeve his sleep study was repeated at home and he no longer required it. He has said that sleeping without a machine was the change he had not anticipated.
A patient who set up her follow-up properly
A patient who had the conversation with her family doctor before travelling, took her written schedule to her first appointment, and has had bloodwork at three, six and twelve months. Her ferritin dropped at six months, her iron was adjusted, and it corrected. That is the system working, and it is why the schedule exists.
Mobility and joint pain
A patient in her fifties with a BMI of 43 and severe knee pain who had been told she was too heavy for knee replacement. Eleven months post-sleeve she had lost enough weight to be listed for surgery. The sleeve was, in her framing, what made the knee possible.
A patient we suggested consider a different route
A patient with a BMI of 36, no associated conditions, who had not tried a structured weight-loss programme. We set out the public referral route, the criteria, and the option of a gastric balloon as a less definitive step. She chose to pursue the public route, and we told her that was reasonable.
Body contouring afterwards
A patient who lost a substantial amount over fourteen months and returned for abdominal and breast surgery once her weight had been stable for eight months. Knowing that option existed from the outset helped her plan, which is why we mention it early rather than late.
18. Questions worth asking any bariatric programme
- “Is a pre-operative endoscopy included?” — the examination that most often changes the plan. A programme that skips it is planning without information.
- “How many days do I stay, and why that number?” — the answer should reference the leak window at days five to ten. This is the most revealing question you can ask.
- “How many nights in hospital, and how many nursing visits afterwards?”
- “Will I see a dietitian, and will I get a written eating progression?”
- “What supplements will I need, and will the prescription be based on my own bloodwork?”
- “What follow-up schedule will I go home with, and will it be addressed to my own doctor?”
- “Will you help me arrange follow-up at home before I travel?” — a programme that engages with this is thinking about your outcome at year five.
- “Given my reflux, is a sleeve the right procedure for me?” — if you have reflux, ask this specifically.
- “What documentation do I take home?” — operative report, endoscopy result, baseline bloodwork, dietary plan, supplementation plan, follow-up schedule.
19. Practical points to know
What to expect
- Less pain than most patients anticipate. The dominant early sensations are shoulder discomfort from the laparoscopic gas, which resolves in a few days, and fullness after very small volumes.
- Fatigue in the first two to three weeks, more pronounced than expected because you are recovering on a very low intake.
- Rapid weight loss visible week to week in the first months. Temporary hair thinning around months three to five, which resolves.
- Portion capacity increasing somewhat after the first year, which is normal.
Recognised points
Sleeve gastrectomy is the most performed bariatric procedure worldwide, with a well-established safety record in properly assessed patients. Your surgeon will discuss the considerations relevant to you, and the ten-day stay with monitoring exists precisely to cover the early ones. The main ones: staple line leak, uncommon, with a characteristic window at days five to ten — the reason for the ten-day stay. Bleeding, most likely in the first days. Venous thrombosis, which is why you are walking within hours, wearing stockings, and taking anticoagulation as prescribed. Stricture, a narrowing of the sleeve, uncommon and treatable endoscopically. Reflux, which can develop or worsen — usually manageable with medication, and the reason the endoscopy matters. Nutritional deficiency, which is preventable with supplementation and detected by the bloodwork schedule. Gallstones, more likely with rapid weight loss. Weight regain, usually modest, and influenced by habits and follow-up. And loose skin, addressed later by body contouring if you wish.

Two things entirely within your control
- Following the pre-operative diet, which makes the operation safer and technically easier.
- Taking your supplements and attending your bloodwork, which is what makes the sleeve a good operation at year ten rather than only at year one.
Stopping smoking
Genuinely important before abdominal surgery. Four weeks before makes a measurable difference to healing and respiratory complications.
Who this suits
Adults meeting the BMI criteria, in a condition to undergo abdominal surgery, who understand that the sleeve is a tool and who are willing to supplement and be followed for life.
Pregnancy
Surgery is not performed during pregnancy, and pregnancy is best deferred twelve to eighteen months afterwards. Contraception in that window needs to be reliable.
20. Price: how it is built and how to compare it
Why we quote per case rather than publishing a price list
Because the workup and the stay vary with your BMI, your conditions and your endoscopy findings. A patient needing a hiatus hernia repair, or requiring more extensive cardiac assessment, has a different plan. Your quote is built from your details, itemised, and fixed once you approve it. See our pricing in Turkey page for how costs are structured.
What determines your price
Five factors.
- The procedure, and whether the endoscopy findings change it — a bypass is a different operation from a sleeve.
- The extent of the workup your BMI and conditions require, including cardiac and respiratory assessment.
- Whether a hiatus hernia repair is included, which is decided at endoscopy.
- The length of your stay — ten days as standard, with nights in hospital and daily nursing afterwards, and longer where you or your surgeon prefer.
- Any condition needing managing around surgery, such as diabetes requiring internal medicine input.
What is included in your quote
Everything in section 16: the online consultation, the full workup including endoscopy, the anaesthetic review, the dietitian consultation and written plan, the surgeon consultation, the procedure, anaesthesia, three to four nights in hospital with continuous monitoring, daily nursing visits for the rest of the ten days, medication including anticoagulation, your supplementation prescription based on your own bloodwork, the final review, complete documentation including a follow-up schedule for your own doctor, help arranging that follow-up, your hotel with full board adapted to your dietary stage, transfers, and your coordinator. A companion is accommodated and fed at no additional cost.
What sits outside it
Flights, travel insurance, your supplements after the initial prescription, your follow-up bloodwork at home, and — if you choose it later — body contouring surgery.
How to compare quotes properly
Five checks, and bariatric quotes vary more in what they include than any other procedure in our series.
- Is a pre-operative endoscopy included? The examination that most often changes the plan.
- How many days is the stay, and how many nights in hospital? Ten days with three to four nights in hospital is the appropriate standard, and a quote based on five days total is not comparable — it is a different level of care during the window that matters.
- Is a dietitian consultation included, and do you go home with a written progression?
- Is a supplementation prescription included, based on your own bloodwork?
- What documentation do you take home? An operative report alone is not enough for a doctor to follow you properly.
Why the lowest quote is rarely the best value
On bariatric surgery, the savings available concern the workup and the stay — and both are the parts that protect you. Omitting the endoscopy saves a morning and occasionally costs a patient the wrong operation. Shortening the stay to five days saves four nights and moves the leak window from a hospital with a bariatric team to a long-haul flight. This is the one procedure in our series where we would say plainly that the cheapest option is not a saving. Ask any programme the two questions in section 18 and compare the answers.
Insurance
Bariatric surgery is available in the public system where you meet the criteria, and care abroad is generally not reimbursed. There is no claim to prepare for the surgery itself. Your follow-up at home is covered as ordinary medical care — bloodwork, physician visits, and any prescribed supplements according to your local formulary. That is worth knowing: the ongoing part costs you little. Travel medical insurance is worth arranging, and read the exclusions carefully — many policies exclude complications of elective surgery, and bariatric surgery specifically in some cases. Ask your insurer in writing, and prioritise medical repatriation and hospitalisation cover.
Payment
A deposit confirms your dates. The balance is settled on site, under terms set out in full when you approve your plan. There are no additional charges once accepted — where the endoscopy findings change the recommended procedure, we discuss the implications and the revised plan with you before proceeding.
Getting your figure
Send your height, weight and BMI, a list of your medical conditions and all medications, your weight history, details of any previous abdominal surgery, and a note of whether you have reflux or heartburn. You will receive a plan and quote within 24 to 48 hours, including whether the sleeve is the right procedure for you or whether another would serve you better.
21. Glossary
- Sleeve gastrectomy — removal of about three-quarters of the stomach, leaving a narrow tube
- Laparoscopic — performed through several small incisions
- Ghrelin — the hunger hormone, produced mainly in the removed portion of stomach
- Restrictive — reduces how much you can eat; the sleeve is restrictive
- Malabsorptive — reduces how much you absorb; the sleeve is not
- Staple line — where the stomach is divided and sealed
- Leak — separation at the staple line; uncommon, with a window at days five to ten
- Upper GI endoscopy — examination of oesophagus and stomach before surgery
- Hiatus hernia — upward displacement of the stomach through the diaphragm; contributes to reflux
- Stricture — narrowing of the sleeve; treatable endoscopically
- Bariatric multivitamin — a supplement formulated for post-surgical needs
- Excess weight loss — the proportion of weight above your target that you lose
22. How patients search for this
- “Gastric sleeve Turkey cost” — the most common search. Ask what the stay and workup include; that is where quotes differ.
- “Gastric sleeve wait time” — frequently years in the public system, which is why most of our patients arrive from a waiting list.
- “Is gastric sleeve covered” — yes, in the public system where you meet the criteria. Ask your family doctor about a referral and the realistic wait.
- “Gastric sleeve vs bypass” — the sleeve for most patients; a bypass where reflux is significant or diabetes severe. Your endoscopy informs this.
- “How much weight will I lose with a gastric sleeve” — a substantial proportion of excess weight over twelve to eighteen months, with realistic figures given at consultation.
- “Gastric sleeve and diabetes” — improvement is frequently rapid and sometimes precedes much weight loss.
- “Gastric sleeve leak symptoms” — the reason for the ten-day stay. Days five to ten is the window.
- “How long to stay in Turkey for gastric sleeve” — ten days. Ask any programme why they say what they say.
- “Gastric sleeve vitamins for life” — yes, and simpler than after a bypass. Your prescription is based on your own bloodwork.
- “Gastric sleeve follow up” — bloodwork at three, six and twelve months then annually, arranged with your family doctor before you travel.
- “Gastric sleeve hair loss” — common around months three to five, related to rapid loss and protein intake, and it resolves.
- “Gastric sleeve reflux” — can develop or worsen. The pre-operative endoscopy is what identifies patients better served by a bypass.
- “Gastric sleeve pregnancy” — possible and common. Wait twelve to eighteen months, and use reliable contraception in that window.
- “Loose skin after weight loss surgery” — body contouring is an option once weight has been stable six months, usually twelve to eighteen months after the sleeve.
In summary: a serious pathway for a definitive operation
Sleeve gastrectomy at Aylan Clinic combines an experienced bariatric team, a full pre-operative workup including endoscopy, a ten-day stay with three to four nights in hospital and daily nursing afterwards, a dietitian programme with a written progression, and a supplementation and follow-up plan built for a patient who lives far away — with 5-star accommodation and a companion at no extra cost, for up to 60% less than private prices at home. Five things that make this go well: have the endoscopy, because it occasionally shows that a bypass would serve you better; stay ten days, because the one serious early complication has a window at days five to ten; follow the pre-operative diet, which shrinks the liver and makes your operation safer; arrange your follow-up before you travel — one conversation with your family doctor; and take your supplements, simpler after a sleeve than after a bypass, lifelong, and the single thing that most determines how well you are at year ten. And ask your family doctor about the public route first — if the wait is manageable, it offers something we cannot, and if it is not, you will have chosen this knowingly.
To go further, see our Gastric Sleeve in Turkey procedure page for how the operation works, the stay and the care, consult our pricing in Turkey page, or explore the full range of bariatric surgery in Turkey.