
UrgoTouch in Tunisia is a laser-based option intended to support the appearance of certain new surgical scars. It is generally discussed at the time an incision is closed, rather than as an operation that reshapes a breast, abdomen or face by itself. The surgeon's incision design, closure technique and ongoing wound care remain central. A Canadian patient comparing clinics should ask whether UrgoTouch is proposed for the particular incision, which surgeon applies it, what additional cost is involved and how the scar will be reviewed over subsequent months.
This page explains UrgoTouch laser treatment, its place in plastic surgery, the available clinical evidence, suitable incisions, alternatives, recovery, travel and pricing. It does not imply that a laser makes a scar invisible or that every patient needs it. The underlying operation and the individual's healing history determine the full plan.
What UrgoTouch is designed to do
A laser applied around surgical closure
UrgoTouch uses a 1210 nm laser approach described as laser-assisted skin healing. The device is applied to selected fresh, closed surgical incisions by a trained clinician according to the product's instructions. Its intended role is to influence the appearance of the resulting scar during healing. It does not close the wound instead of sutures, remove excess skin, change the breast's shape or replace a tummy tuck. Ask which exact incision will receive the treatment and whether the whole length can be addressed. The operation remains the primary procedure; laser use is an adjunct.
The idea behind early treatment
Scar appearance develops through wound healing and remodeling over months. A controlled laser application near the time of surgery aims to influence that process early rather than wait until a mature scar is visible. This is distinct from later laser resurfacing, steroid injections, revision surgery or silicone-based care, which address different situations or phases. The timing and technique should follow the manufacturer information and the surgeon's assessment. A fresh incision is biologically active, but that does not guarantee that an added treatment will outperform careful conventional care for every patient.
What the evidence can and cannot show
A randomized controlled trial published in Aesthetic Plastic Surgery in 2017 studied 1210 nm laser-assisted healing with one-year scar assessment. It provides evidence for a specific technique in a studied population, but an individual patient should ask whether their operation, incision location, skin type and healing factors are comparable. Study averages do not mean every segment improves, and the study cannot prove that any surgeon's closure or aftercare can be replaced. Manufacturer photographs can illustrate possible appearances; they should not be used as a promise of an invisible scar.
Why the name may appear in several operations
A surgeon may discuss UrgoTouch after breast reduction, breast lift, abdominoplasty, arm lift or another operation that creates a suitable closed incision. The length and tension of these scars differ. A short incision behind an ear, a circular areolar scar and a long lower-abdominal incision do not heal identically. Ask whether the clinician has practical experience with the same operation and whether use of the laser changes the planned closure or only adds a step. Its value is judged against the scar care that would otherwise be provided.
Understanding the scar before choosing an adjunct
Where an incision lies and why it matters
Scars are affected by location, direction relative to skin tension, wound edge alignment and the movement of the body part. An abdominoplasty scar beneath clothing, a breast lift scar at the areola and a visible arm scar create different concerns for patients. The surgeon should draw the planned incisions during consultation and explain their probable location in standing and sitting positions. An adjunct does not move a scar into a hidden site. If a patient dislikes the necessary scar location, reconsider the underlying procedure before debating a laser.
Closure, tension and tissue quality
The operating surgeon decides how to align and support wound edges. Tissue circulation, prior scars, body habitus, nicotine use, medicines and tension influence healing. UrgoTouch is not a way to compensate for an incision under excessive tension or an infection. Ask whether an operative technique, scar placement or staged plan can reduce tension before adding a laser. A technically sound operation and practical postoperative support remain the foundation of scar care. Photographs taken immediately after closure tell little about the eventual appearance.
Personal history of prominent scars
Tell the surgeon about previous raised, widened, darkened or slow-healing scars, and show photographs if available. A personal or family tendency toward hypertrophic or keloid scarring may change expectations and follow-up. These terms have different meanings; a scar that is red at an early stage is not automatically a keloid. UrgoTouch cannot guarantee prevention of a scar tendency. The surgeon may discuss other preventive or treatment options depending on the site and history, and a dermatologist or specialist might be useful for an established abnormal scar.
Different skin tones and pigmentation
Post-inflammatory color change and scar contrast can vary among skin tones. The team should discuss the product's instructions, the relevance of clinical evidence to your skin, and how pigmentation will be monitored. Sun exposure and normal maturation also influence color over time. Do not infer that a lighter or darker before-and-after photo represents a device effect without comparable lighting and timing. A realistic goal may be a less conspicuous scar, not the absence of any line. Personalized follow-up is particularly valuable when pigmentation is the principal concern.
Where UrgoTouch may fit in a surgical plan
Breast operations
Breast augmentation, reduction, lift and reconstruction involve different incision patterns, tension and healing timelines. A small inframammary incision cannot be evaluated using expectations for a long inverted-T scar. Ask the surgeon to identify the proposed laser-treated segments on a drawing and show the incision expected from the breast operation itself. Breast shape, symmetry and sensation are determined by the surgical plan, not by UrgoTouch. If a scar treatment is included in a package, ask its separate price and rationale instead of assuming that every part of the scar will look alike.
Abdomen and body contouring
A tummy tuck or body lift may leave a long scar in an area that moves when a patient stands, sits or bends. Scar quality matters, but removal of tissue, closure tension and recovery from the main operation dominate planning. Ask whether UrgoTouch is proposed for the full incision or selected sections, and how the clinician handles corners or junctions. Long incisions require practical care after returning home; a one-time laser application does not remove the need for dressings, review and gradual activity as instructed.
Arms, thighs and other visible sites
An arm or inner-thigh incision may be exposed or may experience significant movement. The decision to add laser treatment should take account of length, healing conditions and the patient's concern about visibility. Clarify whether the incision lies in a crease, along the inner limb or elsewhere, and compare realistic photographs after adequate healing. One device cannot ensure that a long scar is less noticeable than a smaller one; length, position and tissue quality still matter. A surgeon should explain the trade-off between greater contour change and scar visibility.
An operation that may not need the device
A small, well-placed incision in a person with a history of fine scars may not justify an add-on. A wound with a particular healing problem may require conventional medical treatment before aesthetic scar optimization is considered. Some patients prefer to assess the scar naturally and decide on later treatment if needed. The surgeon should explain why immediate laser treatment is suitable for this wound and what plan would be followed without it. There should be room to decline an elective adjunct without changing the necessary surgical care.
| Question | Why it changes the decision |
|---|---|
| Which operation is planned? | The main procedure determines the incision and recovery. |
| Which segments receive laser? | Not every wound or scar location is identical. |
| Who applies the treatment? | Training and timing belong in the plan. |
| What is my scar history? | Prior healing helps set expectations. |
| What care follows closure? | A laser does not replace routine wound care. |
| What does the quote separate? | The adjunct should have a clear cost and rationale. |
From surgery to scar maturation
Preoperative examination and consent
First decide whether the planned surgery itself suits your goal. Review prior scars, health conditions, medication, smoking or nicotine use and anticipated closure sites. Ask the surgeon to describe the incision and closure, then whether UrgoTouch is appropriate. The written consent should identify the treatment's purpose, timing, site, alternatives and extra fee. The clinician should confirm whether the device can be applied to the incision actually created, which may differ from the drawing after operative findings.
What happens at the end of the operation
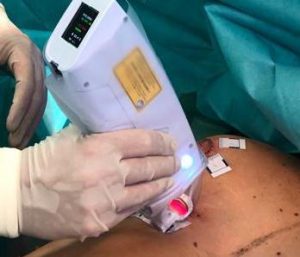
Once the underlying operation and closure are complete, the team may apply the laser to selected incision areas using the device-specific technique. Ask whether this is done in the operating room and whether any dressing or protective step follows. It is usually a single planned application at this stage, but the surgeon should confirm the actual protocol and whether any other postoperative treatment is expected. It should not be sold as an excuse to shorten observation after the original surgery.
The first weeks of care
A newly closed incision may be pink, tender or covered by a dressing. Follow instructions for cleaning, dressing changes, movement and medications from the operating team. If silicone care, sun protection or scar massage is later advised, ask when the wound is ready; do not apply products to an unhealed incision independently. The laser does not remove restrictions imposed by a breast operation or body lift. Keep direct postoperative reviews in Tunisia and know whom to contact after returning to Canada.
Months rather than days
Scar maturation takes time. Early color and firmness can change substantially; a judgment made before the incision settles may be misleading. Agree on photography intervals, using the same lighting and angle, and compare the full length of an incision rather than the best segment. If a scar becomes raised, painful, wide or otherwise concerning, ask for hands-on review and a diagnosis before choosing another laser or revision. Later treatment options depend on whether the concern is color, thickness, width or contour.
How to compare options for scar care
Meticulous closure and standard aftercare
Every patient needs appropriate surgical technique and written care, regardless of whether a laser is used. Ask about scar placement, deep support of the wound, tension management and the schedule of review. Conventional measures may include silicone products after closure, sun protection and treatment of a healing problem when appropriate. The clinician should explain what is included in standard care and which added benefit they expect from UrgoTouch for your incision. If no added benefit is plausible, the device need not define the operation.
Laser treatment at a later date
Lasers used months after surgery can target redness, texture or a raised area depending on the clinical diagnosis. They are not interchangeable with a device used on a fresh incision at closure. If you already have a mature scar, ask for an assessment of that scar rather than booking UrgoTouch by name. Similarly, if you expect to undergo a new operation, ask whether immediate treatment is relevant to the new incision instead of your older mark. The timing of treatment determines the appropriate clinical question.
Revision or treatment of a problematic scar
A scar that widens from tension, remains raised or crosses an awkward contour may be managed with different methods after sufficient healing. Possibilities depend on the cause and might include observation, topical care, injection, another laser or surgical revision. No single intervention fixes every scar type, and an additional procedure creates a new healing process. Discuss both the likely gain and the new scar pathway. A Canadian clinician may need to examine the scar after travel before a responsible recommendation is made.
Practical scar planning for Canadian patients
Know which scar you are paying to treat
A single operation can create several incision lines. Breast surgery may include a periareolar, vertical and fold component; abdominal surgery may include a low horizontal line and a new umbilical opening. Ask whether UrgoTouch covers all of these, only a long segment or none if surgical findings change. Compare a price per incision with a price for the full procedure, including the length and number of applications. A clear diagram and itemized estimate prevent confusion when a photograph of the operation shows more marks than the advertised treatment described.
Keep expectations tied to the main surgery
A smaller, well-positioned scar from a suitable operation may matter more than applying a laser to an unnecessarily long incision. Conversely, when a larger excision is required to address a fold, refusing the right operation solely to avoid a visible scar can leave the central concern untreated. Discuss the contour gain and scar trade-off first. Only then consider whether an adjunct might improve the scar appearance. A scar optimization tool should support a sound surgical plan, not become the reason to choose that surgery.
Organize a photographic review
Before surgery, record the location of older scars, skin tone and your usual response to healing. After surgery, take standardized photographs only as the clinician directs. Similar light, distance and posture make a comparison more meaningful. Note what products and dressings were used and when, since these affect interpretation. Ask the team when they review scar color, texture, thickness and width. If part of the incision differs, share images of the whole wound and a close view rather than selecting a single attractive or worrying spot.
Plan care across two countries
A wound needs direct evaluation if it changes unexpectedly, even when a laser adjunct was used. Before departure, ask who checks the incision in Tunisia, when the surgeon will provide written records and what support is available after you return to Canada. A remote photo may help routine follow-up but cannot answer every question about tenderness, warmth or separation. Make a local clinical contact part of the travel plan. The underlying procedure determines when flying, luggage handling, work and exercise are sensible.
Matching scar care to the exact incision
A short hidden incision
When the line lies beneath a breast or behind an ear, the natural fold may already make it discreet. Ask what additional benefit the surgeon expects from laser application compared with precise closure and routine care. Even a hidden scar can widen or pigment, so the conversation remains individual. A patient who rarely sees the line may decide that the expense offers little value; another with a difficult scar history may value an adjunct. Both decisions require an accurate description of the incision and realistic improvement.
A long incision under movement
An arm, thigh or abdominal scar moves with ordinary activities and may experience variable tension along its length. Ask whether the entire incision is suitable for treatment or whether certain junctions require different care. A photo of the best-healed short segment cannot represent a long wound. Discuss how the main operation's restrictions, dressing changes and weight bearing will protect the closure. UrgoTouch scar treatment does not cancel activity limits or ensure that every centimeter matures alike.
An incision crossing different skin zones
Skin color, thickness and friction can change along a breast or body-contouring incision. The resulting scar may look different around a curve, beneath a garment edge or at a point where several lines meet. Ask the surgeon to describe the segments most likely to be visible and the reason a laser would be used at each. A photograph should show the full pattern from multiple angles. This helps distinguish a difference in appearance caused by anatomy from a difference that an adjunct might reasonably influence.
A previous scar beside the new one
Some patients return for revision or another operation near an older mark. Ask whether the old scar will be excised, left in place or crossed by a new incision. Applying an immediate postoperative laser to the newly closed line does not automatically treat the older scar. If the goal is to improve both, the surgeon should give a separate diagnosis and method for each. Bring operative notes or photographs from the earlier procedure to make the scar map and total quote clear.
Cost of a personalized surgery and optional UrgoTouch laser in Tunisia
An itemized quote should identify every proposed procedure, not simply a package label. Ask for separate surgical fees, anaesthesia, facility, observation, tests, dressings, garments, prescriptions and planned postoperative visits. An optional laser step adds a separate question about which fresh incisions it treats and what it costs. The underlying operation sets most recovery needs. For someone travelling from Canada, total cost includes flights, companion travel when needed, lodging close to the clinic, absence from work and a flexible return booking.
| Cost element | Questions to put in writing |
|---|---|
| Exact operations and sites | Which operation, incision lengths and laser-treated segments are included? |
| Surgeon and anaesthesia | Who performs each step and provides assessment and monitoring? |
| Facility and observation | Where is surgery performed and is an overnight stay proposed? |
| Tests and specialist input | Which examinations are included or billed separately? |
| Dressings and supplies | What is provided, fitted, taught and reviewed after discharge? |
| Local travel and accommodation | How close are recovery lodging and follow-up appointments? |
| Flights from Canada | Allow for connections, companion, luggage help and changes. |
| Extended stay and complications | Clarify the emergency pathway, exclusions and extra treatment costs. |
| Later stages or revision | Confirm whether these are separate operations and quotes. |
Currency changes, work absence and a delayed journey can materially change the final cost. Ask about refunds if the surgeon recommends a smaller operation or postponement. Canadian provincial coverage and private insurance for elective treatment abroad or a complication should be checked individually. A written price without the same procedure scope and follow-up as another quote is not a reliable comparison.

Comparing Tunisia with other treatment locations
| Issue | Tunisia | Canada | Another destination |
|---|---|---|---|
| Direct assessment | Arrange in-person examination before a final procedure plan. | Local consultations may be easier if available. | Clarify timing and access to the actual surgeon. |
| Operating scope | Map each area, scar and staged or combined component. | Compare a clinically equivalent plan. | Check what the surgical and laser package actually contains. |
| Travel burden | Long flight and possible connections during recovery. | Often less travel, though remote communities may still face long trips. | Compare the real itinerary and ground legs. |
| Total cost | Include facility, follow-up, time off and flexibility. | Ask for an itemized equivalent quote. | Account for currency and aftercare at that location. |
| Continuity | Obtain records and arrange a Canadian assessment pathway. | Local reviews may be easier to coordinate. | Plan the handover for the specific destination. |
A country name is not evidence of an individual's skill or a facility's suitability. Compare the named surgeon, exact operation, realistic recovery burden and access to follow-up. A short package itinerary or low initial price can omit a later stage, scar revision or the support needed to care for fresh incisions.
Tunisian cities and postoperative logistics
Tunis: align consultations and recovery
Tunis may offer a workable base if the identified surgeon, anaesthesia team, operating facility and postoperative visits are genuinely located there. Confirm the physical address of each appointment and how far the lodging is from a direct wound check. A named emergency facility and transport plan matter during early recovery. Do not choose an airport or accommodation before confirming where the clinical team actually practices.
Sousse and Monastir: verify the full pathway
Sousse or Monastir can be considered when the specific team performs the operation there and can offer direct follow-up in the same location. Ask whether consultations, surgery, garment fitting and review take place in one city, and how an unexpected issue would be assessed. A resort location does not make the first postoperative days a holiday. Moving between cities can add strain when several areas are healing, so plan lodging around the actual care pathway.
How to choose a surgeon and a plan
Check the named clinicians and facility
Ask for the surgeon's full name, specialty, right to practise, experience with comparable anatomy and the operating facility. Confirm who performs the operation, who provides anaesthesia and who reviews you after discharge. A coordinator can arrange logistics, but clinical questions require direct access to the responsible clinician. Ask whether emergency assessment is available outside office hours and how complications are documented. Verify that any before-and-after photographs are relevant to the same operation and show the incision as it heals.
Ask for a map of the proposed work
A useful consultation examines the planned incision, existing scars and tissue quality, together with health and personal goals. Request a drawing of the planned incisions and a written list of included and excluded procedures. Ask why the laser is added to an operation and which incision each step addresses. A credible surgeon can explain what will remain, the likely scar and when a plan should be narrowed or delayed. A polished package name alone gives none of these answers.
Confirm the handover before booking
Establish who can examine a wound during the Tunisian stay, when the surgeon will assess travel fitness and how the operative report will be delivered. Identify a Canadian clinician or service able to inspect a concern if needed, while recognizing access differs by community. Clarify policies on extra care and later revisions without treating a revision promise as a guarantee. Direct follow-up, records and realistic recovery help make a remote operation understandable and manageable after the patient goes home.
Planning a medical stay in Tunisia
For UrgoTouch in Tunisia, begin with a preliminary history and direct discussion of the proposed surgery rather than selecting flights from a standard package. Send relevant photographs, prior operation records, medicines and travel constraints, while recognizing that only an in-person examination can confirm anatomy and suitability. Reserve time for consultation, anaesthesia assessment, surgery, observation, wound checks and a possible delay before the flight. Plan the return itinerary and access to Canadian care before paying non-refundable costs.
Medical preparation in Canada
Disclose previous anaesthesia difficulties, clot history, chronic conditions, nicotine use, prescriptions and supplements. Ask the surgeon and anaesthesiologist which examinations are necessary and do not stop medicine independently. Arrange practical help at home, especially if daily tasks or lifting will be limited. Check exclusions in health and travel policies for elective surgery abroad. Confirm passport, entry and transit requirements for the actual route. Keep a medical summary and a contact for the Canadian clinician who might provide care after return.
Direct examination and consent
The surgeon should assess tissue quality and the specific areas of concern in person, confirm where incisions would lie and review alternative operations or postponement. The anaesthesia team should determine whether the proposed extent suits your health. Request consent in a language you understand, and verify whether the surgeon and anaesthesiologist themselves can discuss care in English or French or provide appropriate interpretation. A plan made from photographs may change substantially; allow time to consider the new proposal before agreeing.
Recovery near the facility
Stay close enough for direct reviews and arrange assistance with meals, bathing, transport and bags. Follow written directions about walking, dressing care, medications, garments and drains if used. Ask who answers an urgent call and which facility can examine you after hours. A journey across a city or sightseeing immediately after the underlying surgery may disrupt early wound care. Keep track of new symptoms and appointments and ask the team to clarify any instruction that is hard to follow at the accommodation.
Examination before the journey home
A clinician should review incisions, swelling, mobility, pain control and individual clot risk against the whole flight and ground itinerary. Arrange airport and baggage help when relevant, and keep the return date changeable. A patient may be able to walk a short distance yet struggle with a long connection or several hours seated. If a wound or another finding needs reassessment, extend the stay instead of treating the ticket as a medical deadline. Airline boarding permission and the treating surgeon's clinical judgment answer different questions.
Continuing care in Canada
Take home a discharge summary, operative report, medication list, wound instructions, scheduled review plan and direct surgical contact. Agree on remote postoperative visits and identify a Canadian clinician for a hands-on examination when needed. Access to planned aesthetic care and urgent services varies by province and community. Share the exact procedure details if a problem develops. For acute chest pain, breathlessness, fainting, major bleeding or a rapidly worsening wound, seek local urgent care immediately rather than waiting for an overseas video response.
Which Canadian cities can patients travel from?
The right comparison is the complete door-to-door itinerary, including the journey back while swollen and tired. Availability and connections depend on actual dates. A longer route may justify more recovery time in Tunisia, a companion, flexible booking, and a medical review before departure. Ask a clinician in Canada in advance whether they can assess a wound or a possible complication, without assuming that a routine public appointment can replace the operating team's follow-up.
Montreal, Quebec City, Laval and Longueuil
Montreal may offer several airport and connection choices, while Quebec City travellers should compare a local departure with ground transport to another hub. For Laval and Longueuil, getting to an airport can appear simple, but the total journey still includes check-in, transfers, waiting and the trip home after landing. Decide whether consultations and written aftercare instructions should be in English or French; verify which language the surgeon and anaesthesiologist actually use for direct medical discussions. Before departure, identify a Quebec-based clinician or service that can assess a wound or new symptom. Save the operative report, medication list and emergency contact in a format that can be shared promptly.
Ottawa, Gatineau, Sherbrooke, Trois-Rivières, Saguenay and Lévis
Ottawa and Gatineau patients may compare airports on either side of their usual travel corridor, while Sherbrooke, Trois-Rivières, Saguenay and Lévis can add a substantial overland leg. A return flight ending at a distant airport is not the end of recovery: arrange a manageable last leg and someone to help with bags. Weather, road conditions and connections can alter the practical duration. Ask who will remove or check dressings if required and where to seek urgent evaluation after arriving home. The language preferred for medical discussions should be stated in advance and confirmed with the individual clinicians involved.

Toronto, Hamilton, Kitchener–Waterloo and London, Ontario
Toronto residents can compare available itineraries, but should allow for the full time between home, the Tunisian facility and home again. From Hamilton, Kitchener–Waterloo and London, Ontario, airport access and the onward ground journey affect fatigue after surgery. Plan enough time away from work for the operation, observation, review and travel, with flexibility if recovery is slower. Arrange an Ontario contact for clinical questions, and understand that an emergency department addresses urgent symptoms but does not automatically provide planned aesthetic follow-up. Keep a clear English or French medical summary, including the exact operations, incision sites and prescribed medicines.
Vancouver, Victoria, Surrey and Kelowna
Western Canadian journeys can involve additional flight segments and long periods seated. Vancouver and Surrey patients should consider ground access and connection buffers; Victoria and Kelowna patients may add another travel leg. Jet lag and disrupted sleep can make the first postoperative days harder, while a rigid return booking may pressure a patient to fly before a surgeon has reviewed swelling or mobility. Compare refundable or changeable travel options and realistic companion availability. Identify a local assessment pathway before leaving British Columbia and confirm how imaging or operative records could be transferred if a complication requires care.
Calgary, Edmonton, Winnipeg, Saskatoon and Regina
For Alberta and Prairie patients, access to a departure airport, layovers and the final trip home are part of the medical plan. Calgary and Edmonton offer different departure options on different dates; travellers from Winnipeg, Saskatoon and Regina should check the entire itinerary, including transit requirements. Ask how long sitting is reasonable for your individual clot risk and what preventive measures your treating team recommends; a scar dressing is not a substitute for an individual travel assessment. After returning, know which local service can assess a suspected infection, leg swelling or unexplained breathlessness without waiting for an overseas video appointment.
Halifax, Moncton, Dieppe, Edmundston, Fredericton, Charlottetown and St. John's
Atlantic routes may require multiple legs and additional travel to reach the departure airport. Halifax patients should compare actual schedules; Moncton, Dieppe, Edmundston and Fredericton travellers should account for driving or regional connections; Charlottetown and St. John's can add another segment. Acadian and other bilingual patients can request French or English documentation and confirm the language used in each direct consultation. Include a buffer for weather and missed connections, and make a plan for returning home without carrying heavy bags. Follow-up access differs across provinces and communities, so identify a realistic local point of care before paying for travel.
Safety and informed consent
Laser use should follow the manufacturer's instructions and an assessment of the fresh incision. Possible issues include discomfort, a color or texture change, heat injury and a scar that still heals more conspicuously than expected. The underlying operation has its own risks and recovery requirements, which usually matter more to travel planning. Ask who applies the laser, how the wound is protected and who examines any changing incision. Rapidly increasing pain, spreading redness or wound separation calls for timely local assessment. Individual consent should cover both the surgery and elective adjunct.
Why plan a coordinated consultation in Tunisia?
Ask Aylan Clinic to name the operating surgeon, show the planned incisions, explain where UrgoTouch might be applied and separate its charge from the surgery. Confirm direct wound checks, records and contact information for after departure. A coordinator can arrange travel and appointments, while the surgeon decides whether the laser fits the final wound. The itinerary should leave room for a change in technique or a delayed return. A useful proposal makes the optional adjunct and the essential surgical aftercare equally clear.
Request an individualized scar plan
Ask Aylan Clinic to show the incision expected from your proposed surgery, identify whether UrgoTouch is appropriate for it and provide the added price and follow-up schedule in writing. An examination and the final operative plan should determine whether the laser is actually used.
For travel from Canada, arrange reviews in Tunisia and a route for examination of a changing scar at home. The aim is a well-planned operation and attentive wound care, with an adjunct only when its expected contribution makes sense.
Clinical and technical sources
- Laboratoires Urgo, UrgoTouch product information. Manufacturer information describes the technology; it is not a personal outcome guarantee.
- Aesthetic Plastic Surgery, randomized one-year study of 1210 nm laser-assisted skin healing, 2017.
- US CDC, medical tourism considerations.
Continue exploring the complete body contouring and aesthetic surgery overview, compare plastic surgery prices in Tunisia, or request a free, personalized quote.
Everything about UrgoTouch Laser Scar Care in Tunisia
Technique, pricing, results and the full patient journey — every detailed answer in our complete guide.